
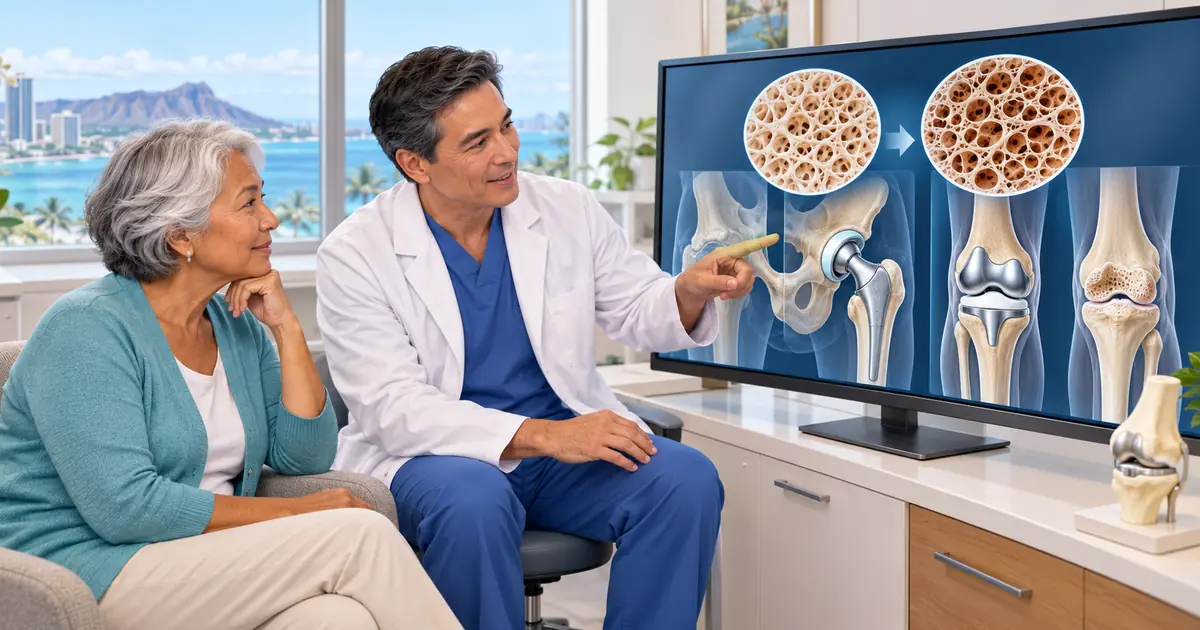
The short answer: osteoporosis changes the plan, not necessarily the decision
Many people with hip or knee arthritis also have osteopenia or osteoporosis. Most can still have a successful replacement when surgery is otherwise appropriate. The important step is recognizing low bone strength early enough to evaluate fracture risk, correct reversible problems, coordinate medication decisions, and plan the operation around the whole patient.
Osteoporosis is not the same as arthritis. Arthritis damages the joint surface; osteoporosis reduces the strength and quality of the bone supporting that joint. A person may have severe arthritis with normal bone density, weak bone with little arthritis, or both conditions at the same time. The replacement decision should still be driven by symptoms, examination, imaging, function, health, and goals—not a bone-density result alone.
Why bone health matters around an implant
A hip or knee implant transfers load through the surrounding bone. Poor bone quality can make that bone more vulnerable to a fracture during a fall, around the time of surgery, or later around the implant. It can also influence how a surgeon thinks about implant fixation, component design, surgical technique, weight-bearing precautions, and fall prevention.
A large database study of total knee replacement patients found that a diagnosis of osteoporosis was associated with higher five-year risks of periprosthetic fracture, aseptic loosening, and some other implant-related complications. That type of observational study cannot prove that osteoporosis directly caused every event, but it supports treating bone health as a meaningful part of risk assessment rather than an unrelated diagnosis.
Osteopenia and osteoporosis are not the same
A DXA scan reports bone-mineral density, usually as a T-score. Osteopenia means bone density is below the young-adult reference range but not low enough to meet the densitometric definition of osteoporosis. Osteoporosis is the more severe range. A prior fragility fracture—such as a hip, spine, wrist, or upper-arm fracture after a low-energy fall—can signal clinically important bone weakness even when the T-score does not tell the whole story.
Bone strength includes more than density. Age, prior fractures, long-term steroid use, smoking, alcohol exposure, low body weight, menopause, kidney or endocrine disease, nutrition, medications, balance, vision, and fall history all affect risk. That is why a questionnaire and medical history are as important as the scan.
Who should ask about bone-density testing before replacement?
Not every person scheduled for joint replacement needs a new DXA scan. Testing is most useful when age, history, or risk factors suggest that the result could change management. National osteoporosis screening recommendations and fracture-risk tools provide a starting point, while the surgical and primary-care teams decide what applies to the individual.
- A prior fracture from a fall at standing height or less
- A previous diagnosis of osteopenia or osteoporosis
- Long-term oral or frequent systemic corticosteroid treatment
- Loss of height, known vertebral compression fracture, or unexplained back pain
- Older age without up-to-date bone-density assessment
- Low body weight, poor nutrition, smoking, heavy alcohol use, or prolonged inactivity
- Conditions or medicines associated with secondary bone loss
- X-rays or operative planning that raise concern about unusually weak bone
Low bone density is commonly missed before elective replacement
In a 2019 study of 200 adults having elective hip or knee replacement, nearly 60% met the study's criteria for DXA testing, yet fewer than one in five of those patients had undergone a recent scan. One quarter met criteria for osteoporosis medication, while only a small fraction received therapy around surgery. The exact percentages will differ across practices and populations, but the message is durable: arthritis care can overshadow bone health unless someone deliberately checks.
Screening is not about creating another obstacle before surgery. It is about finding a risk that may be improved and avoiding the surprise of discovering osteoporosis only after a fracture.
What a bone-health evaluation may include
The evaluation should be proportional to risk. It may include review of prior DXA results, fracture history, family history, current osteoporosis medicine, kidney function, calcium and vitamin D intake, nutrition, tobacco and alcohol use, exercise, and fall risk. A clinician may order a new DXA scan, calculate fracture risk, or obtain laboratory tests when secondary osteoporosis or a nutritional problem is possible.
The goal is not to chase a perfect laboratory number before treating a disabling joint. It is to identify abnormalities that are clinically meaningful, correct what can reasonably be corrected, and coordinate the timeline with the operation.
Do not start or stop osteoporosis medicine on your own
Bisphosphonates, denosumab, anabolic medicines, and other osteoporosis therapies work differently and have different dosing schedules. The best choice depends on fracture risk, kidney function, previous treatment, dental and medical history, and the planned procedure. Evidence about the ideal timing of individual medicines around elective arthroplasty continues to evolve.
Do not skip denosumab, stop a bisphosphonate, or begin a new bone-building medicine solely because surgery is scheduled without speaking to the prescribing clinician and surgeon. Abruptly changing some therapies can create its own risk. Coordination among orthopedics, primary care, endocrinology, rheumatology, or an osteoporosis specialist is often more useful than a blanket rule.
Calcium, vitamin D, protein, and exercise support the plan
Bone and muscle need adequate nutrition, but supplements are not a substitute for diagnosing osteoporosis. Your clinician may review vitamin D and calcium intake, especially when diet, malabsorption, kidney disease, or a prior deficiency raises concern. Excess supplementation is not automatically better and can be inappropriate for some people.
Protein intake and resistance exercise also matter because stronger muscles improve mobility and reduce falls. Before surgery, safe strengthening, balance work, and prehabilitation can prepare the body for recovery. After surgery, activity should progress according to the operative plan and physical-therapy guidance.
How bone quality can influence surgical planning
Implant fixation is individualized. Cemented components, cementless components, stems, augments, screw fixation, or other design choices may be considered according to anatomy, bone quality, deformity, age, activity, and the specific hip or knee. A DXA score alone does not select the implant.
The surgeon also uses ordinary X-rays, examination, intraoperative feel, and the pattern of bone loss. In a hip replacement, femoral and acetabular bone quality can affect preparation and fracture precautions. In a knee replacement, the strength of the distal femur and proximal tibia matters when bone cuts and implant fixation are performed. The practical question is not “Is cement always better?” or “Is cementless always better?” It is which construct gives this patient the most reliable fixation.
Will osteoporosis delay joint replacement?
Sometimes optimization should occur before an elective operation, but osteoporosis does not create an automatic waiting period. A short delay may be reasonable when there is an untreated metabolic problem, severe nutritional deficiency, a recent fragility fracture, very high fracture risk, or another issue that could materially improve with coordinated treatment. In other cases, proceeding with an adapted surgical plan is appropriate because pain, immobility, and deconditioning also carry harm.
The decision should balance the urgency of the arthritis disability against the likely benefit of additional evaluation or treatment. A vague instruction to “fix the bones first” is less useful than a specific plan: what is abnormal, what will be done, who is managing it, and whether the result will change the timing or technique.
Fall prevention remains important after a successful replacement
A replaced joint can work well and still be injured by a fall. A 2024 study of patients treated for periprosthetic hip fractures found that most injuries followed a fall from standing height, yet osteoporosis evaluation and treatment remained uncommon. The lesson is not that replacement causes osteoporosis. It is that fracture risk continues after arthritis pain improves.
Review medications that cause dizziness, improve lighting, clear trip hazards, use railings or grab bars, address vision and footwear, and follow the recommended walker-to-cane progression. If a low-energy fracture happens around an implant, it should trigger both fracture treatment and a systematic bone-health evaluation.
What to bring to your joint-replacement visit
Bring the information that turns “weak bones” into an actionable risk assessment:
- Your most recent DXA report, including the date and measured sites
- A list of prior fractures and how each injury happened
- Every osteoporosis medicine you have taken, with dates and reasons for stopping
- Current calcium, vitamin D, steroid, thyroid, seizure, reflux, and other relevant medicines
- Recent laboratory results if you have kidney, endocrine, nutritional, or absorption problems
- Your fall history, walking aid, and any dizziness or balance concerns
- Your hip or knee X-rays and the activities arthritis prevents you from doing
Questions worth asking before surgery
A focused conversation should produce decisions, not just a label.
- Does my history suggest that I need a DXA scan or fracture-risk assessment?
- Would the result change the operation, implant fixation, or timing?
- Should another clinician manage my osteoporosis before or after surgery?
- Should any current bone medicine be continued, delayed, or rescheduled?
- Are calcium, vitamin D, protein, or other laboratory issues relevant in my case?
- What fall-prevention and mobility plan should I use after discharge?
- If surgery should wait, what specific target are we trying to reach?
The bottom line
Osteoporosis is a risk factor to understand and manage—not an automatic reason to deny someone a needed hip or knee replacement. The safest plan connects arthritis severity, fracture history, bone density, medical causes of bone loss, medication timing, implant strategy, nutrition, strength, and fall prevention.
Dr. Paul Morton evaluates the painful joint and the bone supporting it before recommending surgery. If you have osteopenia, osteoporosis, a prior fragility fracture, or concern about weak bone, bring your DXA report and medication history to an orthopedic consultation or call (808) 439-6201. The goal is a clear, coordinated plan—not an unnecessary delay.
Sources and further reading
- Osteoporosis and Total Knee Arthroplasty: Higher 5-Year Implant-Related Complications
- Osteoporosis Is Common and Undertreated Prior to Total Joint Arthroplasty
- A Novel Osteoporosis Screening Protocol to Identify Orthopedic Surgery Patients for Preoperative Bone Health Optimization
- Systemic Osteoporosis and Osteopenia Among Periprosthetic Fractures After Total Hip Arthroplasty
- AAOS position statement: Osteoporosis and Bone Health in Adults
Medically reviewed by Paul Norio Morton, MD, FAAOS, FAAHKS. Last reviewed: . This article is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.