
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
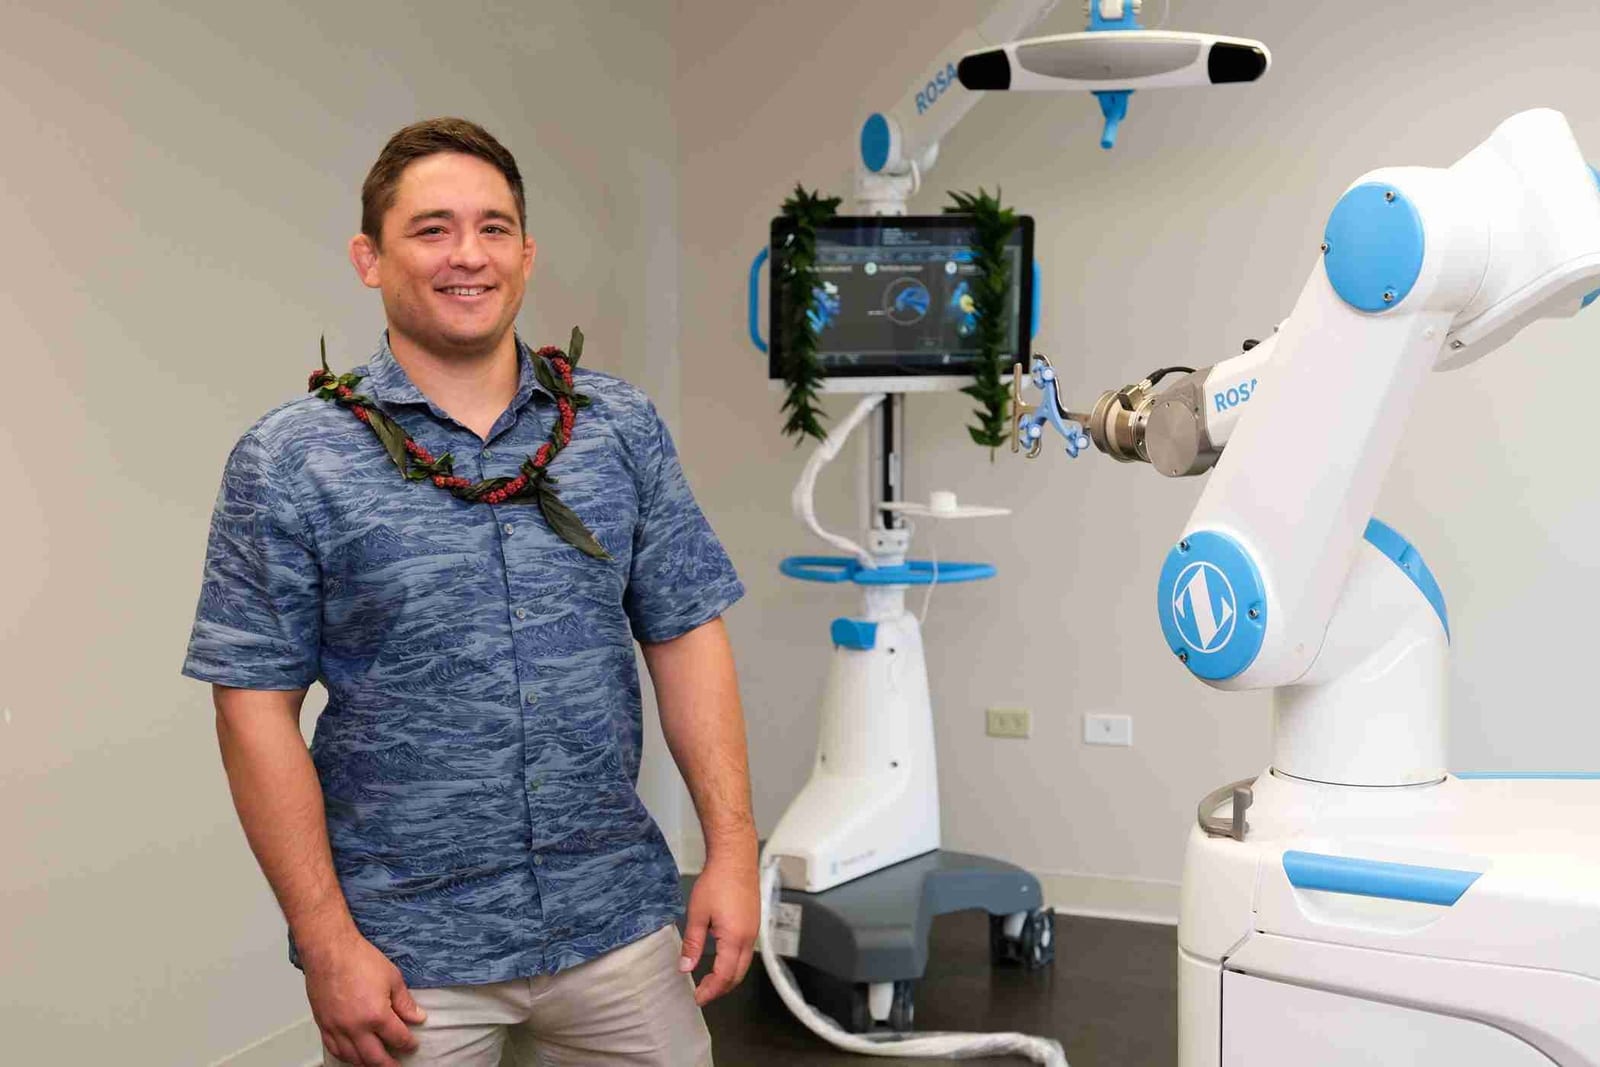
Robotic knee replacement in Hawai‘i — the short answer
Robotic knee replacement is a total knee replacement planned in 3D and executed with a robot that positions the cutting guides and measures ligament balance — the surgeon still makes every cut and every decision. It is for anyone who is a candidate for knee replacement. Dr. Morton uses it on every knee, through a 4–6 inch quad-sparing incision, without a tourniquet. Most patients walk the same day and are home within 24 hours. Individual results vary.
- Planning: a personalized 3D model from standard X-rays — no CT scan, no extra radiation
- Incision: 4–6 inches, versus 10–12 with traditional instruments
- Who operates: Dr. Morton — the robot never cuts on its own
- Platforms: certified on ROSA®, Mako, CORI, and VELYS; Mako on the Big Island
- Recovery headline: walking the same day, home within 24 hours for most
What does "minimally invasive" really mean?
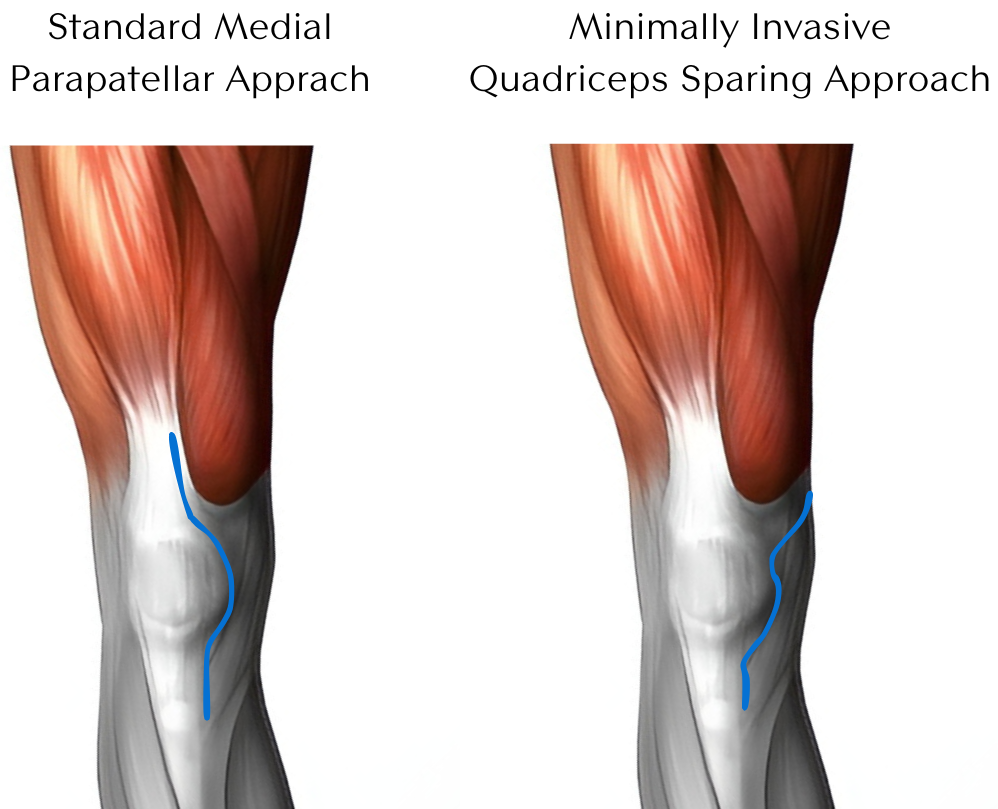
Minimally invasive knee replacement means less damage on the way to the joint — a 4–6 inch skin incision instead of the traditional 10–12 inches, and, more importantly, less disruption of the muscle and soft tissue underneath. The implant you receive is a full total knee replacement; what changes is how gently your body is treated getting there.
The skin incision is the visible part, but it is not where the recovery benefit comes from. Early-recovery advantages track with how the deeper tissues are handled: a subvastus approach that never divides the quadriceps tendon, a tourniquet-free technique so the thigh muscle is never crushed under a pressurized cuff, and cuts planned so that fewer soft-tissue releases are needed. One of Dr. Morton's patients, photographed five months after a robotic total knee, stood beside a scar from a traditional knee replacement done years earlier by another provider — the newer incision was roughly half the length. That is a single case, not evidence; the evidence is in how the muscle underneath was treated.
There is an honest trade-off with any smaller exposure: less room to see means less margin for error in positioning the implant. Robotic tracking is what makes the small window safe — every cut is planned, guided, and verified against the plan rather than eyeballed — though no technology removes the need for surgical judgment. Traditional instrumentation also lines up the cuts with metal jigs, including a rod passed down the center of the femur; robotic guidance replaces that hardware with optical tracking, so the bone canal is never instrumented.
How ROSA® robotic assistance works
ROSA® builds a personalized 3D model of your knee from standard X-rays — no CT scan, no extra radiation, no added imaging cost. Before the first incision, Dr. Morton has already planned your implant size, position, and alignment on that model.
In the operating room, ROSA tracks your knee in real time and positions cutting guides to match the plan within fractions of a degree. It also measures something the human eye can't: how your ligaments tension and balance through the full range of motion. That data lets Dr. Morton fine-tune the implant to your ligaments rather than forcing your knee to match a one-size-fits-all jig. To be clear about roles — the robot never cuts on its own. It is a precision instrument in the hands of a surgeon who makes every decision.
- More data collected during surgery than any surgeon could gather by eye
- Real-time information on implant size, alignment, and ligament balance
- Better-informed surgical decisions as the operation unfolds
- Ligament balance optimized and objectively verified
- Implant position personalized to your anatomy
- Consistent leg alignment from patient to patient
- Safer bone cuts, checked for accuracy after they are made
Planning your knee before the first incision
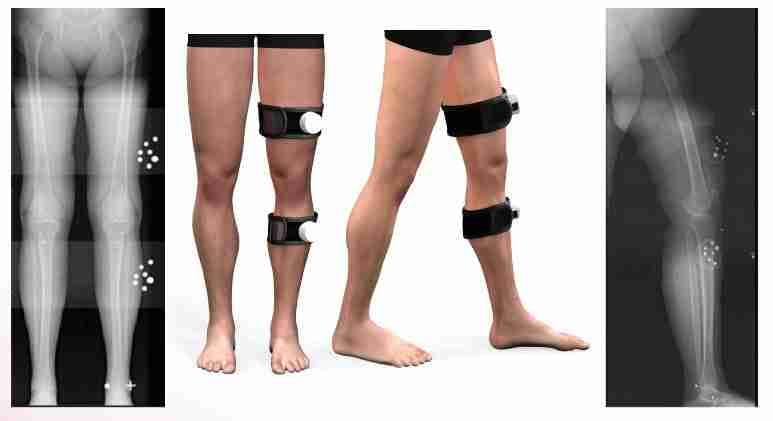
Robotic knee replacement begins days before surgery. Some robotic platforms plan from a CT scan or long-leg standing films; ROSA uses standard X-rays taken with special calibration markers that allow accurate measurement of your alignment and deformity. From those images, a preoperative plan is personalized to your knee before you ever enter the operating room.
That planning pays off in concrete ways:
- Accurate implant sizing in advance — less guesswork during surgery and a shorter operation
- Your deformity measured before surgery — so the correction is planned, not improvised
- A personalized blueprint — implant size, position, and alignment decided on your 3D model, then refined in the OR with live ligament data
Dr. Morton is certified on all four robotic platforms — ROSA®, Mako, CORI, and VELYS — so the technology is matched to your knee and your surgical venue, not the other way around. On the Big Island, he operates with the Mako robot at Hilo Community Surgery Center, bringing the same robotic precision to patients in Hilo and Kona without a flight to O‘ahu.
Robotic knee replacement, step by step
Patients often ask what the robot actually does during surgery. Here is the operation as Dr. Morton performs it:
- Step 1
Navigation pins and calibration
Small navigation pins are placed so the robot can track the exact position of your bones throughout the operation.
- Step 2
Exposure of the joint
The joint is opened through the smaller, quad-sparing window. The soft-tissue releases often required in conventional surgery usually are not needed.
- Step 3
Mapping your landmarks
Dr. Morton traces the landmarks of your knee with a tracked instrument, building a real-time map of your anatomy.
- Step 4
Measuring soft-tissue balance
The robot records how your ligament gaps open and close through motion — information unavailable in a conventional knee replacement.
- Step 5
Finalizing implant position
With your anatomy and ligament data on screen, the final implant position is confirmed before a single cut is committed.
- Step 6
Robot-guided bone cuts
The robot positions the cutting guides and Dr. Morton makes the cuts; each cut is verified against the plan after it is made.
- Step 7
Placing your new knee
The components are fixed in the planned position and alignment and balance are confirmed one final time before closing.
Robotic vs conventional knee replacement: what actually differs
Knee replacement is one of the most successful operations in medicine, yet about 20% of patients remain dissatisfied with some aspect of a traditionally performed knee. Imbalance and malalignment are the usual suspects — and they are exactly the variables robotic assistance measures and controls.
| Conventional (jig-based) | Robotic (ROSA®) | |
|---|---|---|
| Incision | Typically 10–12 inches | Typically 4–6 inches |
| Planning source | Standard X-rays and intraoperative jigs | Personalized 3D model from calibrated X-rays, refined live in the OR |
| CT scan needed | No | No — ROSA plans from plain X-rays (some other platforms use CT) |
| Alignment | Mechanical jigs, including a rod down the femoral canal | Optical tracking; cuts positioned and verified within fractions of a degree |
| Ligament balancing | Estimated by feel | Measured through the full range of motion and adjusted before cutting |
| Tourniquet | Usually inflated for the whole operation | None in Dr. Morton's protocol |
| Discharge | Commonly one to several nights | Same day to one night for most of Dr. Morton's patients |
The numbers behind the table: in a published review of 788 consecutive total knees performed in Honolulu with conventional instruments (Andrews et al., The Journal of Arthroplasty, 2019), a neutral mechanical axis was achieved in 86% of patients — roughly one in seven missed the ±3° target even in experienced hands. A meta-analysis of 29 studies (Mason et al., The Journal of Arthroplasty, 2007) found malalignment over 3° in about 32% of conventional knees versus 9% with computer assistance. And in a cadaveric accuracy study of the ROSA Knee system (Parratte et al., The Journal of Arthroplasty, 2019), the average difference between the planned and executed cut angles was under one degree, with resection thickness within a millimeter of plan. Precision is what the evidence shows most clearly — alignment and balance are the factors linked to durability and a natural-feeling knee, and the surgeon's training still matters more than any machine.
Why precision changes your recovery
Accuracy is not an abstraction — it shows up in how you feel. When cuts follow a verified 3D plan, fewer soft-tissue releases are needed, ligaments are balanced instead of stretched, and the implant sits in the alignment that decades of research link to durability and a natural-feeling knee.
It also matters for satisfaction. Imbalance and malalignment are among the usual suspects behind the one-in-five dissatisfaction rate described above — and they are precisely the variables robotic assistance measures and controls. That is why Dr. Morton uses it on every knee, not just the difficult ones.
- Smaller incision with less soft-tissue injury
- Ligament balance measured objectively, not estimated
- Alignment planned in 3D and executed within fractions of a degree
- Less early pain, so less need for opioid medication
- Walking the same day; home within 24 hours for most
- Precise alignment supports long-term implant survival
Are you a candidate for robotic knee replacement?
Any patient who is a candidate for a total knee replacement is a candidate for a robotic knee replacement — including knees with significant deformity, where 3D planning is often most valuable. Prior hardware or unusual anatomy occasionally changes the plan, and Dr. Morton will always choose the approach that keeps your surgery safe and your implant precisely positioned. The technology serves the outcome — never the other way around. Whether your knee is ready for replacement at all is a separate question, answered in full on the total knee replacement page and the guide to alternatives to knee replacement.
"With robotic knee replacement, I believe we're able to place our patients' implants more accurately, with less soft-tissue injury and a faster recovery." — Dr. Paul Morton
- You may be a candidate if standing X-rays show bone-on-bone arthritis and nonsurgical care — injections, anti-inflammatories, exercise — has failed
- You may be a candidate if knee pain is taking away daily living, leisure, work, or time with people you love
- You may be a candidate if your knee has deformity or prior surgery — 3D planning often helps most here
- It may be too soon if your arthritis is mild on X-ray or you have not tried nonsurgical care
- It may be the wrong operation if arthritis is confined to one compartment — a robotic partial knee may fit better
Trained for this — first in Hawai‘i
Robotic surgery is only as good as the surgeon planning it. Dr. Morton was the first surgeon in Hawai‘i fellowship-trained in robotic joint replacement, and he has since performed a series of state firsts: the first robotic-assisted total hip replacement in Hawai‘i, the first robotic joint replacement on Hawai‘i Island, and the state's first Persona IQ® smart knee. He is certified on four robotic platforms — ROSA®, Mako, CORI, and VELYS — which means the technology is chosen to fit your knee, not the other way around.
Robotics is one layer of a complete rapid-recovery protocol. The others: the quad-sparing subvastus approach, tourniquet-free surgery that spares you thigh pain, iovera° cryoneurolysis for drug-free nerve pain relief lasting up to 90 days, targeted post-operative nutrition designed for joint replacement healing, opioid-sparing anesthesia, and a same-day discharge program for eligible patients.
Recovery, risks, and the rest of the story
Robotics is one layer of the operation, and this page deliberately stays on that layer. What a total knee replacement actually replaces, when it is time to consider one, what the recovery timeline looks like week by week, and the risks stated plainly are all covered on the total knee replacement page; the month-by-month playbook is in the knee replacement recovery guide.
The short version: most patients walk the day of surgery, most are home within 24 hours, sedentary work returns around six weeks, comfortable walking by about three months, and strength keeps building past a year. Physical therapy is available at Dr. Morton's Honolulu and Kunia clinics. Individual results vary — a precise plan improves the odds, it does not guarantee the timeline.
Talk with Dr. Morton about robotic knee replacement in Honolulu
Dr. Morton is one of the few orthopedic surgeons in Hawai‘i fellowship-trained in hip and knee reconstruction. He performs robotic total knee replacements, partial knee replacements, and revision knee replacements at The Queen's Medical Center — which holds Advanced Certification for total hip and total knee replacement from The Joint Commission — at Adventist Health Castle, and at Hilo Community Surgery Center, home of the Big Island's Mako robot.
If knee pain is limiting your life, schedule an orthopedic consultation at any of Dr. Morton's four Pacific Bone & Joint clinics — Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo, or Kona — or call (808) 439-6201. Most new patients are seen within one to two weeks. Bring a photo ID, your insurance card, a list of current medications, and any prior imaging or operative reports; if your X-rays were taken in Hawai‘i, the office can usually retrieve them electronically, and new standing X-rays are taken in the clinic at the same visit. Managed-care and Medicaid/Quest plans may need a referral from your primary care physician — the office checks before your visit. When an in-person visit isn't practical — a neighbor island without a nearby clinic, or a patient traveling from across the Pacific — a telehealth visit with existing X-rays can start the process. Consultations are conducted in English, and interpreters can be arranged.
Medically reviewed by Paul N. Morton, MD, FAAOS, FAAHKS — board-certified orthopedic surgeon, fellowship-trained in adult hip & knee reconstruction and orthopedic trauma. Last reviewed: .
This page is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.