
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
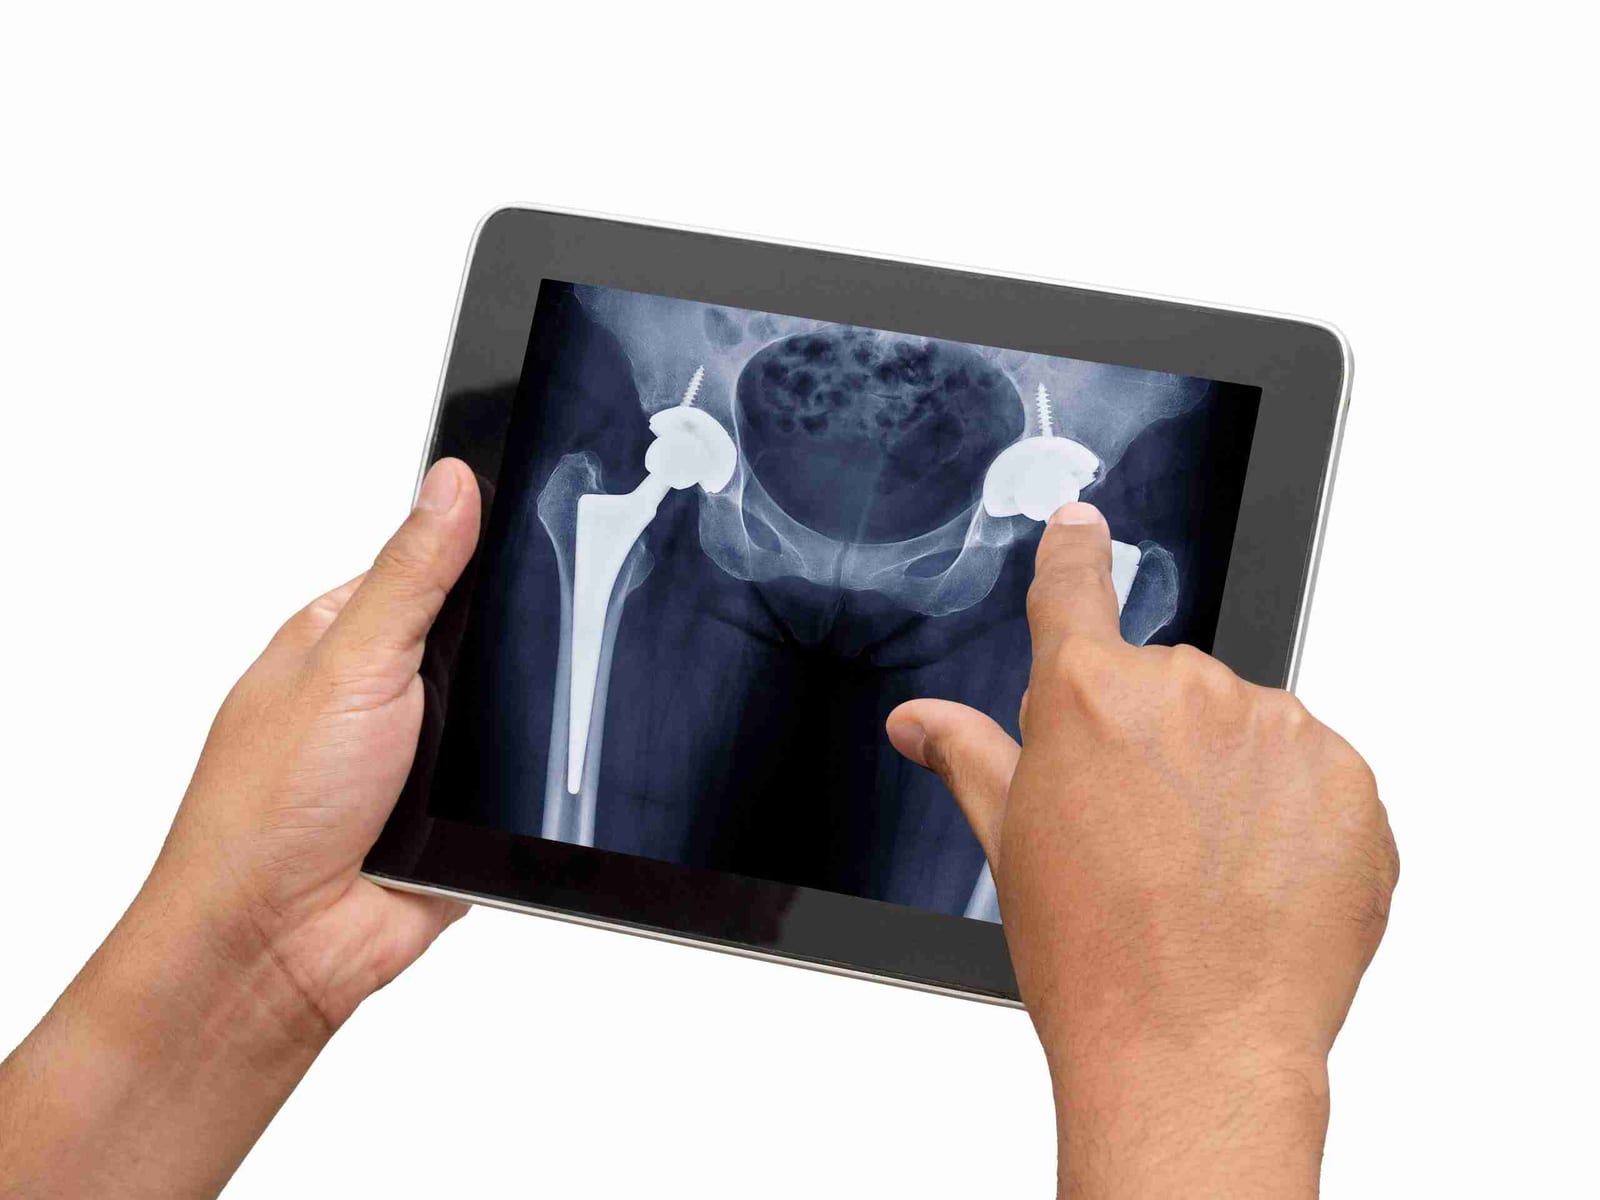
Hip replacement in Honolulu — the short answer
Total hip replacement replaces the arthritic ball and socket of the hip with a metal, ceramic, and polyethylene implant. It is for people whose hip arthritis, avascular necrosis, or fracture causes pain that therapy, medication, and injections no longer control. In Honolulu, Dr. Paul Norio Morton — founder of Pacific Bone & Joint — performs every hip with robotic guidance through the muscle-sparing direct anterior approach, and most patients walk the day of surgery. Individual results vary.
- Approach: muscle-sparing direct anterior — no muscle detached from bone, usually no hip precautions
- Guidance: robotic 3D planning with real-time verification of cup position and leg length on every hip
- Incision: 3–6 inches at the front of the hip, with a bikini-incision option along the groin crease
- Recovery: walking the day of surgery, home the same day or after one night for most, driving at about 2–4 weeks
- Longevity: modern implants commonly last 20 years or more, with lifetime implant surveillance built in
Are you a candidate? When a hip needs replacing
A hip needs replacing when the cartilage lining the ball-and-socket joint is worn away and nonsurgical care — activity changes, anti-inflammatories, injections, therapy — no longer controls the pain. The three most common reasons are osteoarthritis, avascular necrosis (loss of blood supply that collapses the femoral head), and hip fracture in bone that cannot be reliably repaired. Inflammatory arthritis and arthritis that develops years after an old injury wear a hip out the same way; if you are still sorting out what your hip is telling you, start with the five common causes of hip pain.
There is no prize for waiting until you can barely walk — severe stiffness and muscle loss make recovery slower, and they are avoidable. It may be too soon if cartilage remains on your X-rays and joint-preserving care has not had a genuine trial; age alone is not a reason to wait. You may be a candidate if:
- X-rays show bone rubbing on bone
- Groin or thigh pain persists despite therapy, medication, or injections
- Pain interrupts your sleep
- Your walking distance keeps shrinking — shorter walks, skipped hikes, avoided stairs
- Stiffness makes putting on shoes and socks a struggle
What a total hip replacement actually replaces
A total hip replacement resurfaces both sides of the worn joint. The damaged femoral head — the ball — is removed and replaced with a ceramic or metal head mounted on a stem that fits securely inside the thigh bone. The worn socket is prepared and fitted with a titanium cup and a smooth, highly durable liner, most commonly a modern cross-linked polyethylene engineered specifically for low wear. Which head and liner materials suit your age and anatomy is covered in hip bearings, explained.
The result is a new bearing that glides instead of grinds. Modern implants are designed so bone grows directly into their textured surfaces; when your bone quality allows, Dr. Morton favors cementless fixation, which relies on that biologic bond rather than bone cement. Component sizes are chosen to restore your hip's natural center of rotation, offset, and leg length — the geometry that lets muscles work efficiently again. The arthritis is gone because the arthritic surfaces are gone.
One operation, three deliberate choices
Ask Dr. Morton which approach he recommends, which incision, or whether the robot is worth it, and the answer is the same for nearly every first-time hip: the method he uses every week. His hip replacement is a single, integrated technique built from three deliberate choices — the muscle-sparing direct anterior approach as the road in, a bikini incision that hides the scar along the groin crease, and robotic guidance on every case for millimeter-level control of cup position and leg length. He performed the first robotic-assisted total hip replacement in the state of Hawai‘i, and the anterior approach is his standard technique — not an occasional offering.
Each choice earns its place for a reason, and the three compound: the approach spares the muscle, the incision hides the evidence, and the robot verifies the result before the incision is ever closed. The sections below tell the story choice by choice — with a deep-dive page on each if you want the full case.
- Muscle-sparing direct anterior approach as his routine technique
- Bikini-incision option for a scar hidden along the groin crease
- Robotic 3D planning and real-time verification on every case
- Cementless implants when bone quality allows
- Opioid-sparing pain control and same-day walking
Why anterior: the road in decides the recovery out
Every total hip replacement does the same core work; what differs is the road in. The traditional posterior approach reaches the joint through the back of the hip, splitting the gluteus maximus and releasing the short external rotators, which are then repaired and must be protected while they heal. The direct anterior approach reaches the same joint from the front, through a natural interval between muscles. No muscle is cut or detached from bone — only the joint capsule is opened — so nothing needs to be repaired.
That one anatomical difference drives almost everything patients notice afterward:
- Less pain. With no muscle cut, some patients need little more than Tylenol in the first days — a natural fit with Dr. Morton's opioid-sparing pain protocol.
- Usually no hip precautions. Posterior-approach patients spend weeks avoiding low chairs, crossed legs, and bending past 90 degrees; anterior patients typically skip those rules.
- Lower early dislocation risk. The stabilizing structures behind the hip are never disturbed.
- Verification is built in. Because the operation is done face-up, live X-ray can confirm cup position and leg length before the incision is closed.
A well-done posterior hip replacement is still an excellent operation, and long-term implant survival is similar across approaches — the difference is the first stretch of recovery. Dr. Morton performs the anterior approach as his standard technique — outcomes depend on a surgeon doing it routinely — and when anatomy or prior surgery makes another approach genuinely safer, he says so.
Deep dive: 6 reasons the anterior approach makes hip replacement recovery easier →
Why the bikini incision: same surgery, hidden scar
The bikini incision is the finishing touch on the anterior approach. Instead of a vertical incision down the front of the thigh, the skin incision is turned to run obliquely along the natural groin crease — the line a swimsuit or underwear waistband follows. Only the skin incision changes: underneath, the deep exposure is the identical muscle-sparing anterior surgery, with the same robotic guidance and the same recovery.
The orientation matters because of Langer's lines, the natural tension lines in your skin. An incision that runs with those lines heals under less tension, so it tends to mature into a thinner, flatter, less visible scar; a vertical incision crosses them and can widen as it matures. The largest published comparison — a 964-patient series in The Bone & Joint Journal (Leunig et al., 2018) — found implant position and revision rates equal to the standard anterior incision, with higher scar satisfaction for the bikini incision. In Hawai‘i, where swimwear is practically a uniform, it is one of the most requested options in Dr. Morton's practice. Skin folds, prior scars, and body shape all factor into planning, and occasionally a standard anterior incision is simply the better surgical choice; Dr. Morton will tell you directly which your anatomy favors.
Deep dive: the bikini incision — an anterior hip replacement that hides its scar →

Why robotic: precision you can measure
In 2022, Dr. Morton performed the first robotic-assisted total hip replacement in the state of Hawai‘i. Today robotic guidance is how every hip in his practice is done — hence the nickname The Robot Doc — and he is certified on ROSA®, Mako, CORI, and VELYS, so the platform is matched to your anatomy, implant, and surgical venue.
The robot does not operate. Dr. Morton performs every step; the robot maps your anatomy into a personalized 3D plan, tracks the hip in real time, and confirms that cup position, implant sizes, and leg length match the plan within millimeters. What robotic guidance measurably improves is accuracy and reproducibility: cup orientation, leg length, and offset land where they were planned, with fewer outliers than hand-held instruments. In a matched-pair laboratory study of a CT-free robotic hip platform (Kamath et al., 2021), 100% of robotically placed cups landed within the target zone, versus 73% with traditional instruments; published meta-analysis likewise credits robotic guidance with better component positioning and modestly better short-term hip scores. The practical payoff is that leg length and offset — the two things patients most often notice afterward — are verified before the incision is closed, rather than discovered later.
Deep dive: robotic hip replacement — the evidence, the platforms, and what the robot actually does →
Planning starts weeks before the incision
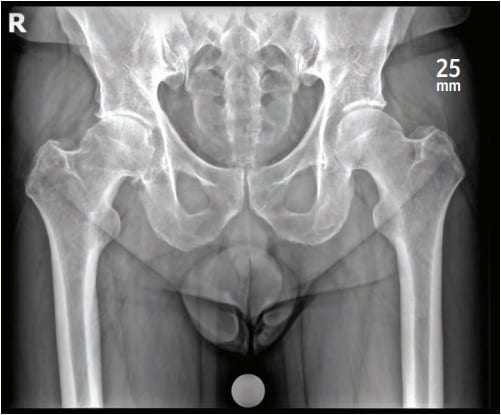
Your hip replacement begins in the weeks before surgery, with a set of X-rays. Pelvis X-rays are taken with a calibration marker — a small reference ball of known size that lets Dr. Morton template your hip precisely, measuring your anatomy and pre-selecting the size and position of your implants before the operation begins.
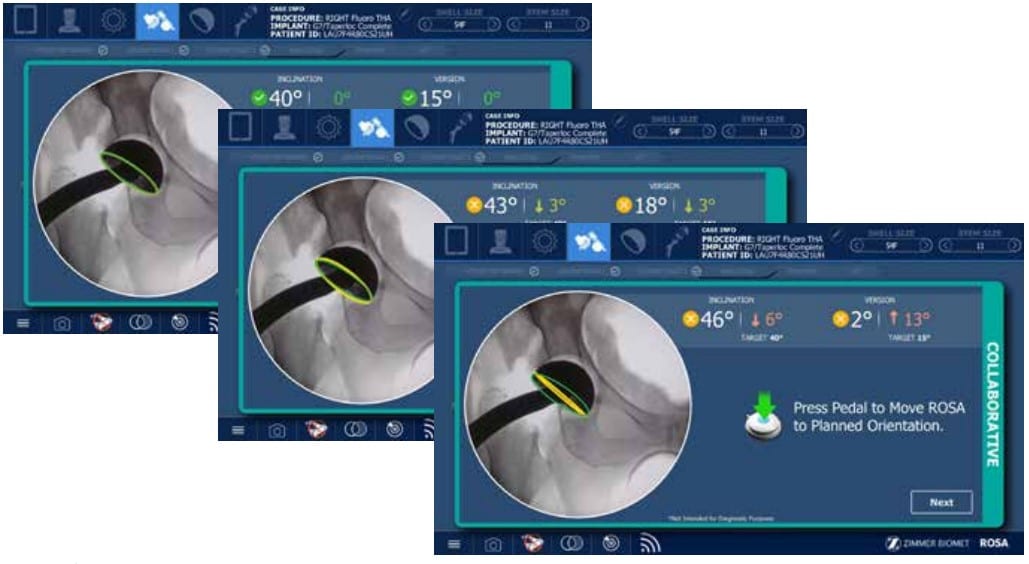
When your hip is planned on Mako — the platform at Hilo Community Surgery Center — a CT scan of your pelvis and hip is added to that work-up, and no IV contrast is needed. The scan becomes a 3D model of your own anatomy, and on that model Dr. Morton sets cup size and position — inclination and anteversion — along with stem size, leg length, and offset before surgery day. In the operating room the robotic arm holds reaming and cup impaction inside that plan, with leg length and offset read out live.
Spine X-rays, taken standing and sitting, evaluate your pelvic-spine relationship. This matters more than most patients realize: arthritis of the spine can change how your pelvis tilts as you move between sitting and standing, which changes the functional orientation of your hip socket. A cup position that is textbook-perfect for one patient's spine can be wrong for another's. Understanding your specific pelvic-spine mechanics lets Dr. Morton personalize the robotic plan — not just hit a generic target.
Your recovery timeline
Most patients stand and walk with a walker within hours of surgery — early movement is the foundation of the whole recovery, and because the anterior approach spares the muscles, most have no formal hip precautions and can move naturally from day one. Around the operation sits Dr. Morton's rapid-recovery protocol: opioid-sparing multimodal pain control that starts before the first incision, no routine urinary catheter or drains for most patients, and physical therapy the day of surgery. Healthy patients often qualify for outpatient joint replacement; others stay a single night. Physical therapy is available through PB&J Physical Therapy, which Dr. Morton founded, at his Honolulu and Kunia locations. The first year after hip replacement walks through every milestone in detail.
| When | What most patients are doing |
|---|---|
| Day of surgery | Stand and walk with a walker within hours; physical therapy the same day; home the same day or after one night |
| Weeks 1–2 | Walk often, control swelling, let the incision heal; many trade the walker for a cane and need little pain medication |
| Weeks 2–6 | Driving once off narcotic medication and able to brake hard (about 2–4 weeks); many walk unassisted indoors by 3–4 weeks; by six weeks most of daily life is back |
| About 3 months | Most everyday activities — walking, swimming, golf, gentle hiking; most patients have stopped planning the day around the hip |
| Months 3–12 | Strength, stamina, and trust in the hip keep building; first annual surveillance X-ray |
Individual results vary; timelines depend on your health, anatomy, and home support.
- Weeks before
Plan in 3D
Calibrated pelvis and spine X-rays let Dr. Morton template implant sizes and personalize cup orientation before surgery.
- Surgery day
Up and walking
Robotic anterior hip replacement, then standing and walking with a walker within hours — home the same day or after one night for most.
- Weeks 1–2
Walker to cane
Walk often, control swelling, let the incision heal. Usually no hip precautions and little pain medication.
- Weeks 2–6
Car keys back
Driving at about 2–4 weeks once off narcotics; many walk unassisted indoors by 3–4 weeks.
- 3 months
Most of normal life
Walking, swimming, golf, and gentle hiking are back for most patients.
- 1 year
Quiet strength
Strength and stamina keep building; annual X-ray surveillance protects the hip for life.
Clot prevention — and when to call the office
Blood clots are the risk every joint replacement protocol takes most seriously in the early weeks. For most healthy patients, prevention means aspirin for several weeks plus frequent short walks; patients with a history of clots or other risk factors are prescribed a stronger anticoagulant instead. Do not stop the medication early without checking with the office.
Most recoveries are uneventful, but a few warning signs deserve a same-day call. Call (808) 439-6201 right away if you notice:
- Fever or chills
- Spreading redness, drainage, or an opening at the incision
- New calf pain or swelling
- Chest pain or shortness of breath — call 911 first
- A sudden inability to bear weight, or a leg that suddenly looks shorter or turned — possible dislocation
- Pain that worsens instead of easing
How long will a hip replacement last?
Modern hip replacements commonly last 20 years or more. In a 2017 Lancet analysis of more than 63,000 hip replacements in the United Kingdom (Bayliss et al.), 85% were still in place at 20 years. Longevity comes down to implant position, fixation, and bearing materials — three variables Dr. Morton controls with robotic planning, cementless fixation in good bone, and modern low-wear bearings. The fourth variable is follow-up, which is why every patient enters a lifetime implant surveillance program: an annual X-ray that confirms the hip is functioning at its best, so small problems caught early stay small — and a revision, if one is ever needed, stays simple. Younger patients put more miles on an implant, which is why age changes the planning conversation, not the eligibility.
A well-positioned hip replacement also tolerates real life: walking, swimming, cycling, golf, and hiking are all encouraged. The American Academy of Orthopaedic Surgeons advises avoiding running, jogging, jumping, and other high-impact activities, which accelerate wear on the plastic components — nearly everything else comes back.
The risks, stated plainly
Total hip replacement has a high success rate and is one of the most reliable operations in all of orthopedics — over 90% of patients get a remarkable reduction in pain and a dramatic improvement in function. It is still major surgery, and informed patients make better decisions. The possible complications include:
- Blood clots — deep vein thrombosis or pulmonary embolism
- Blood loss — occasionally enough to require a transfusion
- Infection — one of the more severe complications; can require multiple operations
- Implant loosening — sometimes requiring revision surgery; a painful hip replacement always deserves a workup
- Fracture — the implant changes how stress distributes across the bone
- Dislocation — when the ball pops out of the socket; addressed with accurate, verified cup placement, the muscle-sparing anterior approach, and spine-aware planning
- Leg-length inequality — minimized by measuring leg length during the operation rather than estimating it
- Heterotopic ossification — a rare complication in which extra bone forms and the hip stiffens
- Nerve or blood vessel damage — extremely rare, but potentially serious; temporary numbness on the outer thigh can occur with the anterior approach and usually fades
Dr. Morton takes great care to minimize each of these risks and is happy to discuss any question or concern before you commit to anything — that conversation is part of the operation, not an afterthought.
Where it happens — and your first visit
Dr. Morton performs hip replacement at The Queen's Medical Center — which holds Advanced Certification for total hip and knee replacement from The Joint Commission — at Adventist Health Castle, and at Hilo Community Surgery Center, where hip replacements are CT-planned and performed with Stryker's Mako robot — a full robotic hip, on the Big Island. The venue is matched to your health, your insurance, and the robotic platform planned for your case.
What happens next. Book an orthopedic consultation online or call (808) 439-6201. Pacific Bone & Joint sees hip patients in Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo, and Kona. Bring a photo ID, your insurance card, a list of your medications, and any prior X-rays, MRI, or operative reports — on-site X-ray is available if you have none. Managed-care and Medicaid/Quest plans may require a referral from your primary care physician; the office can help you check before your visit (see insurance plans accepted). Neighbor-island and mainland patients for whom an in-person visit isn't practical can start with a telehealth visit and existing X-rays. You will leave with a diagnosis, honest options, and a plan, whether or not that plan includes surgery.
Medically reviewed by Paul N. Morton, MD, FAAOS, FAAHKS — board-certified orthopedic surgeon, fellowship-trained in adult hip & knee reconstruction and orthopedic trauma. Last reviewed: .
This page is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.