
The short answer: alignment is a clue, not the whole diagnosis
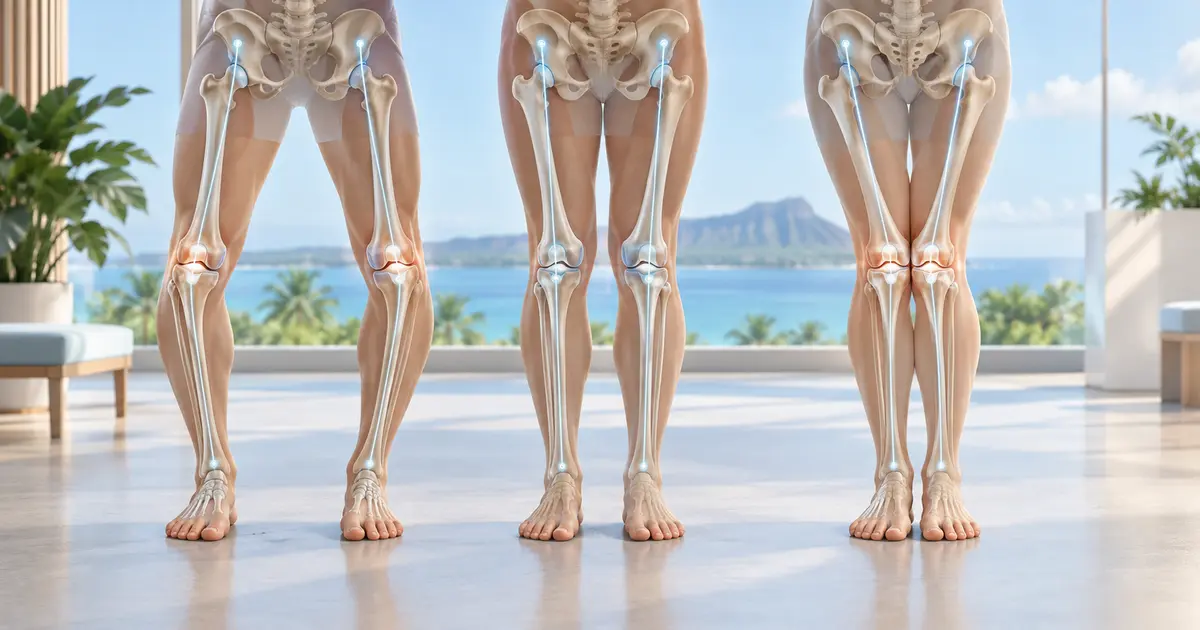
Doctors use varus for a bow-legged alignment and valgus for a knock-kneed alignment. Those terms describe direction. They do not, by themselves, tell you how much pain you should have or whether an operation is needed.
Some people have lived comfortably with the same leg shape for decades. Others notice that one knee is gradually bowing outward or falling inward as cartilage wears, bone remodels, and ligaments stretch or tighten. The important question is not “Does my leg look straight?” but “What is causing the change, how is it affecting the joint, and is it limiting the life I want to live?”
Varus versus valgus: what the words mean
In a varus knee, the knee sits farther from the body’s midline than the hip and ankle, producing the familiar bow-legged appearance. Arthritic wear commonly concentrates in the medial, or inner, compartment. In a valgus knee, the knee angles toward the midline, producing a knock-kneed appearance, and wear often concentrates in the lateral, or outer, compartment.
Real knees are more complicated than a front-view label. Rotation, flexion contracture, bone shape, foot position, hip anatomy, old fractures, and ligament balance can all change what you see. That is why photographs or a short knee X-ray cannot replace a standing examination of the whole leg.
Did alignment cause the arthritis—or did arthritis change the alignment?
The relationship can run in both directions. A lifelong bow-legged or knock-kneed shape may load one compartment more heavily over time. Arthritis can then deepen that imbalance as cartilage and bone wear unevenly. In other patients, an injury, childhood growth problem, prior surgery, or fracture changes the limb first; in still others, joint-space loss is the main driver.
The distinction matters because the deformity may come from the femur, the tibia, the joint itself, or several places at once. A good plan identifies the source instead of assuming that every apparent bow or knock is corrected in the same way.
Why full-length standing X-rays matter
Routine weight-bearing knee X-rays show how much space remains between the bones and which compartments are worn. A full-length standing image adds the hip and ankle, letting the surgeon trace the overall load-bearing axis through the limb. Side and kneecap views add information about motion, flexion contracture, and patellofemoral arthritis.
These images are interpreted together with your gait and physical examination. The surgeon asks whether the deformity is flexible or fixed, whether the knee fully straightens, which ligaments are tight or loose, and whether the hip, spine, ankle, or opposite leg is contributing to the way you stand.
When bow-legged or knock-kneed arthritis needs treatment
Treatment is driven by symptoms and function, not appearance alone. Early or moderate arthritis may be managed with activity changes, strength work, weight management when relevant, medication, injections, and sometimes an unloading brace. Those measures can reduce pain and improve function even though they do not permanently reshape an arthritic adult leg.
A replacement discussion becomes reasonable when pain or instability limits walking, stairs, work, sleep, or valued activities; imaging confirms advanced joint damage; and well-chosen nonsurgical care no longer provides acceptable relief. Review the broader hip and knee arthritis decision framework before treating the X-ray rather than the person.
Does deformity automatically mean total knee replacement?
No. The operation must match the pattern of disease. If arthritis is truly isolated to one compartment and the ligaments, motion, and deformity meet the right criteria, a partial knee replacement may be considered. When wear involves several compartments, the deformity is fixed, or ligament balance is compromised, total knee replacement is more likely to provide a stable reconstruction.
There is no safe online angle cutoff that decides this for everyone. Standing images, examination, age, activity goals, bone quality, and the condition of the other compartments all matter. A visibly bowed knee may still be flexible; a modest-looking valgus knee may have complex ligament imbalance.
What knee replacement changes
Total knee replacement removes a thin amount of damaged surface from the femur and tibia, positions metal components on those prepared surfaces, and places a smooth bearing between them. For a deformed knee, the work also includes restoring a stable joint line and balancing the soft tissues through the range of motion.
The goal is a comfortable, durable, stable knee—not a cosmetic promise that every limb will look mathematically identical. Dr. Morton’s personalized alignment approach starts with each patient’s anatomy, then uses the boundaries of safe implant position and ligament balance to build the plan.
Why more correction is not always better
Historically, many knee replacements were planned toward a common neutral mechanical target. Contemporary alignment strategies also consider the patient’s original joint line, bone shape, and soft-tissue envelope. The essential safeguard is to avoid trading one imbalance for another.
A 2024 study found that patients whose preoperative varus knees were corrected across neutral into valgus had worse early knee scores and temporarily reduced motion compared with knees kept neutral or in residual varus. That single observational study does not dictate one target for every patient, but it reinforces a useful principle: correction should be deliberate and balanced, not simply “as straight as possible.”
Can severe varus or valgus deformity still be replaced?
Often, yes. Severe deformity makes planning and execution more demanding because bone loss, contracture, stiffness, and ligament imbalance may be greater. The surgeon may need different component sizes, stems, augments, soft-tissue balancing steps, or a more constrained implant depending on what is found.
Published 2024 studies report meaningful correction and functional improvement after total knee replacement in severe varus and valgus knees. These are not guarantees for an individual patient. They show that difficult alignment is a planning challenge, not an automatic reason to accept disabling arthritis without evaluation.
Where robotic assistance may help—and where it does not
Robotic systems can help the surgeon map bone anatomy, measure alignment and ligament gaps, plan component position, and verify the cuts during surgery. A 2024 comparative study found improved coronal alignment, sagittal component position, and early recovery with robotic assistance in severe varus or valgus deformity, while advantages were not substantial in mild deformity.
That does not mean the robot chooses the target or performs the operation independently. AAOS guidance reports no proven short-term functional or patient-reported advantage for robotic over conventional total knee replacement overall. Technology can make measurements more reproducible; judgment still determines which measurements make sense for your knee. Learn how ROSA robotic knee replacement fits into that workflow.
What to bring to an alignment-focused consultation
A useful evaluation looks beyond the most recent knee film. Bring prior X-rays if available so the surgeon can see whether alignment is changing. Also bring details about old fractures or operations, childhood leg conditions, braces, injections, physical therapy, and where pain is actually felt.
- Current weight-bearing knee X-rays and any prior films for comparison
- A list of treatments tried and how long each helped
- History of fractures, ligament injuries, or operations on the hip, knee, tibia, ankle, or foot
- Examples of the activities pain or instability now prevents
- Questions about partial versus total replacement
- Your home, work, caregiving, and Neighbor Island travel needs
- Medication list and relevant medical history
Questions worth asking before surgery
The best questions connect the visible deformity to the complete plan:
- Where does my deformity come from—the femur, tibia, joint wear, ligaments, or more than one place?
- Is the alignment flexible or fixed when you examine me?
- Which compartments are arthritic on weight-bearing views?
- Would a partial replacement be appropriate, or is total replacement more reliable?
- What alignment target are you planning, and why does it fit my anatomy?
- How will ligament balance be checked through the range of motion?
- Would robotic assistance materially help with my particular deformity?
- Does the opposite hip, knee, ankle, or spine affect the plan?
- What recovery limits should I expect because of stiffness or deformity?
When a change in alignment needs prompt evaluation
Gradual bowing with arthritis is usually evaluated in clinic, but some changes should not wait. Seek urgent assessment after a fall or injury if the leg suddenly changes shape, you cannot bear weight, or severe pain and swelling develop. A hot, red knee with fever, new calf swelling, or sudden shortness of breath also needs prompt medical attention.
Progressive deformity without an acute emergency still deserves evaluation when it is accompanied by instability, repeated falls, rapidly declining walking tolerance, or pain that is no longer controlled by the current plan.
The bottom line
Bow-legged and knock-kneed alignment can help explain where an arthritic knee is wearing, but the visible shape is only the beginning of the workup. Full-length standing images, weight-bearing knee views, motion, ligament balance, symptoms, and goals together determine whether nonsurgical care, partial replacement, or total replacement makes sense.
Dr. Paul Morton evaluates the entire limb and builds knee-replacement alignment around the patient rather than a photograph alone. To review your standing images and options, schedule an orthopedic consultation or call (808) 439-6201.
Sources and further reading
- AAOS: Surgical Management of Osteoarthritis of the Knee clinical practice guideline
- Journal of Arthroplasty: Avoiding correction from varus across neutral into valgus
- Journal of Clinical Medicine: Outcomes after total knee arthroplasty in severe varus deformity
- BMC Musculoskeletal Disorders: Robotic-assisted total knee arthroplasty in severe varus or valgus deformity
Medically reviewed by Paul Norio Morton, MD, FAAOS, FAAHKS. Last reviewed: . This article is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.