
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
Hip and knee arthritis treatment in Hawai‘i — the short answer
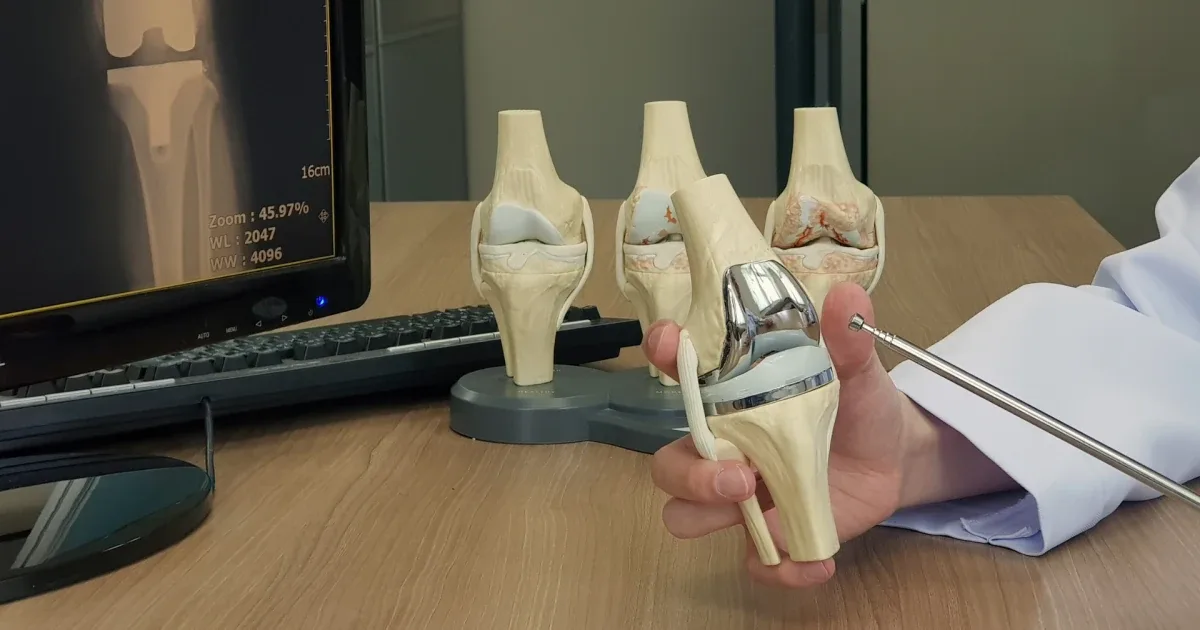
Hip and knee arthritis treatment is a ladder, not a switch: strengthening and weight optimization first, then medication, injections, biologics and nerve treatments, and joint replacement only when the joint is bone-on-bone and pain is stealing your life. Dr. Paul Morton, a fellowship-trained hip and knee surgeon in Honolulu, stages every joint with standing X-rays and an honest exam — and most of his arthritis patients never need surgery.
- Staging first: weight-bearing X-rays and an exam determine your rung in one visit — there is no blood test for osteoarthritis
- Five types are treated here — osteoarthritis, rheumatoid and other inflammatory arthritis, gout, post-traumatic, and septic — and the label changes the treatment
- Twelve non-surgical options, from physical therapy in-house at Ala Moana and Kunia to injections, PRP, BMAC, and iovera°
- Robotic partial or total replacement — most often same-day — when conservative care has genuinely failed
- Clinics in Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo and Kona — (808) 439-6201
What arthritis actually is
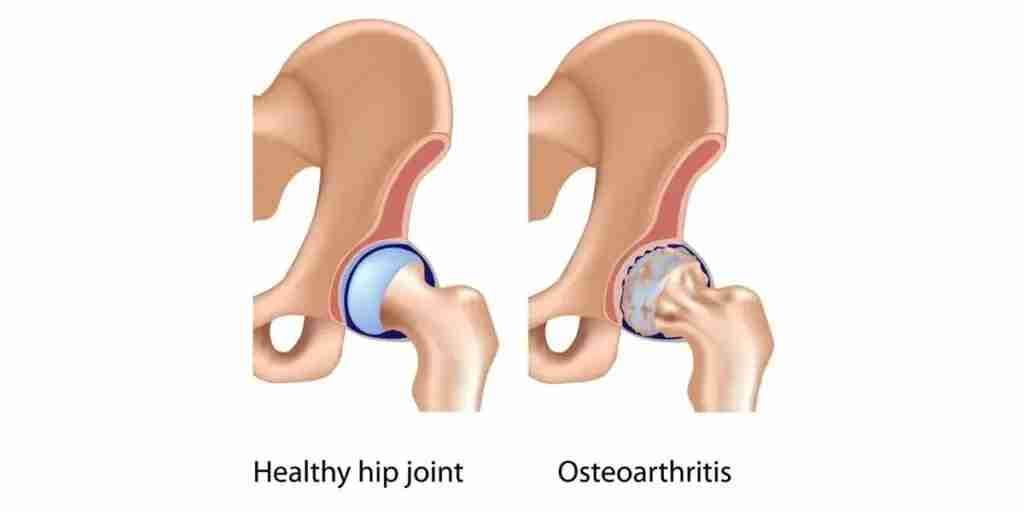
A joint is simply the connection between two bones, and healthy cartilage is the smooth bearing surface that lets those bones glide past each other without friction. Arthritis means that cartilage is wearing away. As it thins, bone begins to grind against bone — and a joint that once moved silently starts to ache, stiffen, and swell. The two joints most often affected are the ones that carry you: the knee (between the femur and tibia) and the hip (between the pelvis and the femur).
It's also far more common — and more costly — than most people realize:
- Nearly one in four U.S. adults (about 23%) lives with doctor-diagnosed arthritis, per the CDC
- It's the leading cause of work disability in the United States, limiting the work of roughly 8 million working-age adults
- It drives more than $140 billion in U.S. healthcare costs every year
- 60% of adults with arthritis are of working age (18–64) — this is not just a disease of the elderly
- The hip and knee are the two joints most commonly affected
The five types — and why the label matters
Osteoarthritis — by far the most common — is mechanical wear over decades. Rheumatoid arthritis and its inflammatory relatives are immune-driven and co-managed with rheumatology (which specialist you need). Gout is a crystal disease of uric-acid metabolism. Post-traumatic arthritis follows old injuries, often decades later. And septic arthritis is joint damage left behind by infection. All five roads can end at the same place — bone on bone — but the pace, the pain pattern, and above all the treatment options differ. Getting the label right is the first job of the first visit.
Osteoarthritis: when wear outpaces repair
Osteoarthritis (OA) is not the same thing as "old age" — plenty of people live long, active lives with pain-free joints. OA develops when cartilage cells become damaged and lose the ability to rebuild. Enzymes released from those damaged cells break down collagen and proteoglycan — the structural building blocks of cartilage — faster than the joint can replace them. Age, genetics, excess weight, prior surgery, and a history of injury all tilt the balance toward breakdown.
As cartilage disappears, the bone beneath it hardens (sclerosis), the joint edges sprout new bone (bone spurs), and fluid-filled pockets called subchondral cysts form in the deteriorating bone. Eventually the joint wears through entirely — the "bone-on-bone" appearance on an X-ray.
The five stages of osteoarthritis
| Stage | What's happening in the joint | What you typically feel |
|---|---|---|
| 0 — Normal | Healthy cartilage, full joint space | Nothing — no pain, no impairment |
| 1 — Minor | Tiny bone spurs begin forming where the bones meet | Usually nothing yet |
| 2 — Mild | More bone-spur growth; cartilage still healthy and joint space preserved | Mild ache after a long, strenuous day; stiffness after sitting too long |
| 3 — Moderate | Visible cartilage damage; joint space significantly narrowed | Frequent pain with walking, running, or bending; extended morning stiffness |
| 4 — Severe | Cartilage nearly gone, joint space drastically reduced, less lubricating fluid — friction with every movement | Pain with nearly every step; a stiff, difficult joint |
How osteoarthritis is diagnosed
There is no blood test for OA — labs are used only to rule out inflammatory causes like rheumatoid arthritis. Standing (weight-bearing) X-rays show the cartilage loss and bone spurs directly, and stage the disease in a single visit. An MRI is rarely required; it's reserved for complex cases where soft-tissue detail changes the plan.
Rheumatoid arthritis: an immune attack on the joint
Rheumatoid arthritis (RA) is a chronic autoimmune disease: the body's own immune system attacks the synovium, the soft-tissue lining that produces the fluid nourishing and lubricating the joint. As the synovium is destroyed, the cartilage and bone beneath it deteriorate, and movement becomes painful. Unlike osteoarthritis, RA can strike at any age, and it can involve far more than joints — skin, lungs, heart, and eyes. The exact cause is still unknown, but identified genetic markers raise the risk roughly fivefold.
The four stages of rheumatoid arthritis
- Stage 1 — Mild: the synovium is inflamed and the joint hurts, but the bones are not yet damaged.
- Stage 2 — Moderate: inflammation begins destroying cartilage; range of motion narrows and movement becomes painful.
- Stage 3 — Severe: bone itself erodes; with the cushion gone, bones rub and wear against each other, and muscle weakness sets in.
- Stage 4 — End-stage: the inflammation may finally burn out, but the joint no longer functions — extreme pain, stiffness, and swelling, and the bones may even fuse together (ankylosis).
How rheumatoid arthritis is diagnosed
Early RA is genuinely hard to pin down — no single finding or lab confirms it. The diagnosis combines the exam with inflammation markers (ESR and CRP), confirmatory antibodies (rheumatoid factor and anti-CCP), and imaging: X-rays to track progression, MRI and ultrasound to gauge severity. Because modern disease-modifying medications have been genuine game-changers, Dr. Morton co-manages inflammatory arthritis with rheumatology — medical control of the disease first, surgery only for the joints already destroyed.
Gout: needle-shaped crystals in the joint
Gout is a disorder of uric-acid (urate) metabolism. Uric acid is a normal byproduct of purine breakdown; trouble starts when the body makes too much of it (metabolic disorders, dehydration) or can't excrete enough (kidney or thyroid problems, inherited conditions). Once blood and tissues are saturated, urate precipitates into hard, needle-like crystals — favoring the cooler, more acidic environment of peripheral joints — that physically grind away at cartilage and bone with every movement.
The attacks are unmistakable: sudden, severe episodes of pain, swelling, redness, and tenderness — classically waking you in the middle of the night with the sensation that your big toe is on fire. Long-standing gout can also deposit visible crystal lumps under the skin, called tophi.
Diagnosis is definitive: fluid is drawn from the joint with a needle (arthrocentesis) and examined under a microscope for urate crystals. Treatment works: urate-lowering medications (allopurinol, febuxostat, probenecid), medications to prevent flares, and dietary changes — cutting back on red meat, organ meats, sugary drinks, and fructose-heavy foods that raise uric acid.
Post-traumatic and septic arthritis
Post-traumatic arthritis
Post-traumatic arthritis develops when a joint that once sustained a physical injury — a car accident, a fall, a sports or military injury — wears out ahead of schedule. The original trauma damages bone and cartilage and deranges the joint's mechanics, so it grinds where it used to glide; excess body weight accelerates the process further. These joints are often the most complex to treat: deformity, retained surgical hardware, and prior operations can make both the arthritis pattern and the eventual surgery more demanding than routine osteoarthritis. X-rays tell most of the story; a CT scan or MRI is added when planning requires it.
Septic arthritis
Septic arthritis is joint inflammation caused by infection — usually bacterial, most often staphylococcus. Bacteria reach the joint through the bloodstream, a penetrating injury, or an infection in nearby bone or soft tissue, and joints with pre-existing arthritis are especially vulnerable. The immune system's battle against the bacteria damages the cartilage itself, so even a cured infection can leave a permanently arthritic joint. Diagnosis rests on lab markers (ESR, CRP) and aspirating joint fluid to test for bacteria. This history matters enormously for later care: patients who have had a joint infection carry a higher risk of chronic pain, and joint replacement after septic arthritis has an elevated risk of failure and re-infection — which makes experienced surgical planning essential.
The ladder, rung by rung
Treatment escalates only as needed:
- Foundation: targeted strengthening, weight optimization (every lost pound removes several pounds of joint load), activity redesign, tai chi and water exercise
- Medication: scheduled acetaminophen, anti-inflammatories used wisely
- Injections: cortisone for flares, hyaluronic-acid gel for lubrication
- Biologics: PRP, BMAC, and A2M for the right joints at the right stage
- iovera°: freezing pain nerves for months of relief without drugs
- Surgery: partial or total replacement — when the ladder below stops working
Twelve ways to treat arthritis without surgery
Treatment for hip and knee arthritis begins without a scalpel — and there is a good chance your pain improves without ever needing one. Here is the full nonsurgical toolkit Dr. Morton draws from:
- Anti-inflammatories (NSAIDs): ibuprofen, naproxen, and relatives reduce both inflammation and pain — effective, but used judiciously
- Acetaminophen (Tylenol): an inexpensive over-the-counter reliever that works on the brain's pain processing rather than the joint itself — a useful scheduled baseline
- Corticosteroid injections: calm an inflamed joint for months at a time; they can be repeated about every three months, and many patients do well on just one or two a year
- Weight management: every pound on your body is roughly four pounds across your knees — modest weight loss pays outsized dividends
- Exercise and physical therapy: building the muscles around the hip and knee shields the joint from load, and stretching restores flexibility — PT is available at the Kunia and Honolulu offices
- Walkers and canes: the right gait aid offloads a painful joint and keeps you moving safely
- Activity modification: jogging on a worn-out joint invites pain and further cartilage damage; trading high-impact activities for swimming or cycling often means a pain-free experience with the same fitness
- Hyaluronic-acid "gel" injections: add cushion and lubrication; FDA-approved for knees; patients who respond often get months of relief at a time, and not everyone responds — a carefully chosen trial is how you find out
- Anti-rheumatic medications: disease-modifying drugs have been genuine game-changers for rheumatoid and other inflammatory arthritis — co-managed with rheumatology
- Anti-gout medications: urate-lowering drugs (allopurinol, febuxostat, probenecid) plus dietary changes stop crystal attacks at the source
- Nerve treatments — radiofrequency ablation and iovera°: heating or freezing the nerves that carry knee-pain signals can deliver drug-free relief lasting months — ablation relief typically lasts six to twelve months, and it can be repeated
- TENS units: surface electrodes deliver gentle electrical stimulation; portable take-home units give some patients meaningful pain control without medications or procedures

Complementary and alternative medicine, honestly discussed
Hawai‘i patients often ask about complementary treatments — and Dr. Morton welcomes the conversation rather than dismissing it. The goal is that you understand what each option involves, what the evidence actually shows, and what it costs, before you spend money on it. Treatments patients commonly ask about include:
- Platelet-rich plasma (PRP) injections — offered in-office where the evidence supports them
- Stem-cell and bone marrow concentrate (BMAC) injections
- Cannabidiol (CBD) and medical marijuana
- Acupuncture
- Chiropractic manipulation
- Massage therapy
- Homeopathy and naturopathic medicine
- Kava (‘awa)
- Turmeric (‘ōlena)
- Glucosamine and chondroitin
Some of these help some patients modestly; none of them regrows cartilage. Bring whatever you're using — or considering — to your visit, and you'll get a straight answer about it.
The mistake patients make in both directions
Half wait too long — grinding through years of shrinking life while the joint (and the muscles around it) deteriorate, making eventual surgery harder. The other half jump too fast, replacing joints that injections and strengthening could have managed for another decade. The antidote to both is staging: standing X-rays, an honest exam, and a surgeon who profits nothing from steering you wrong. Dr. Morton's practice is deliberately built on the whole ladder, so the recommendation matches the joint — not the business model.
- Step 1
Standing X-rays + exam
Weight-bearing films taken in clinic the same day show cartilage loss, spurs, and alignment; labs only to rule out inflammatory disease.
- Step 2
Type and stage named
Osteoarthritis stage 0–4, inflammatory, crystal, or post-traumatic — and whether wear is one-compartment or joint-wide.
- Step 3
Lowest rung that works
Strengthening, weight, medication, injections, biologics, or iovera° — matched to the stage, not the business model.
- Step 4
Re-stage when relief shrinks
When each treatment buys less time and pain limits work, daily life, family, or the things you love, replacement is discussed.
Are you a candidate for joint replacement — or is it too soon?
The page's own criteria, turned into a checklist. Neither list is a diagnosis; both are settled by standing X-rays and an exam in a single visit.
- You may be a candidate if: X-rays show bone-on-bone (stage 4) arthritis
- You may be a candidate if: a proper trial of conservative care — strengthening, weight optimization, medication, injections — no longer controls the pain
- You may be a candidate if: pain is limiting your work, activities of daily living, relationships with family, or the activities you love
- You may be a candidate for a partial knee if: the wear is confined to one compartment and the ligaments are intact — see partial knee replacement
- It may be too soon if: the joint still shows cartilage on standing X-rays (stages 1–3)
- It may be too soon if: you haven't done structured strengthening, or a single well-timed injection still buys months of relief
- It may be too soon if: the diagnosis is inflammatory, crystal, or septic arthritis that hasn't yet been medically controlled
When replacement becomes the right answer
Three signs, together, usually mean it's time: bone-on-bone imaging, failed conservative care done properly, and — most important — pain that's stealing your life. Dr. Morton puts it to patients in concrete terms: he considers surgery when conservative treatment has failed and pain is limiting one or more of four areas of life.
- Your ability to work — when pain keeps you from your job, even on light-duty tasks.
- Activities of daily living — when the grocery store, or simply moving around your own house, has become an ordeal.
- Relationships with family — when constant pain makes you short-tempered, or keeps you from playing with your grandchildren.
- The activities you love — when golf, tennis, biking, or beach walks are off the table. In his words: "Life is not worth living if you cannot enjoy the things you like to do."
When those align, modern hip replacement and knee replacement are a remarkably good trade: robotic precision (Dr. Morton is certified on all four major platforms — ROSA, Mako, CORI, and VELYS), muscle-sparing approaches, same-day discharge, and implants that commonly last 20+ years; individual results vary. Until they align, every other rung gets used first.
Not sure which rung you're on? Your next step
Not sure which rung you're on? An exam and weight-bearing X-rays settle it in one visit — book a consultation or call (808) 439-6201; clinics in Honolulu (Ala Moana), Kunia, Hilo and Kona, with most new patients seen within one to two weeks. Bring a photo ID, your insurance card, a medication list, and any prior imaging; managed-care and Medicaid/Quest plans need a referral from your primary care physician, which the office helps arrange. Telehealth works for staging when an in-person visit isn't practical, with standing X-rays taken near home.
Medically reviewed by Paul N. Morton, MD, FAAOS, FAAHKS — board-certified orthopedic surgeon, fellowship-trained in adult hip & knee reconstruction and orthopedic trauma. Last reviewed: .
This page is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.