
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
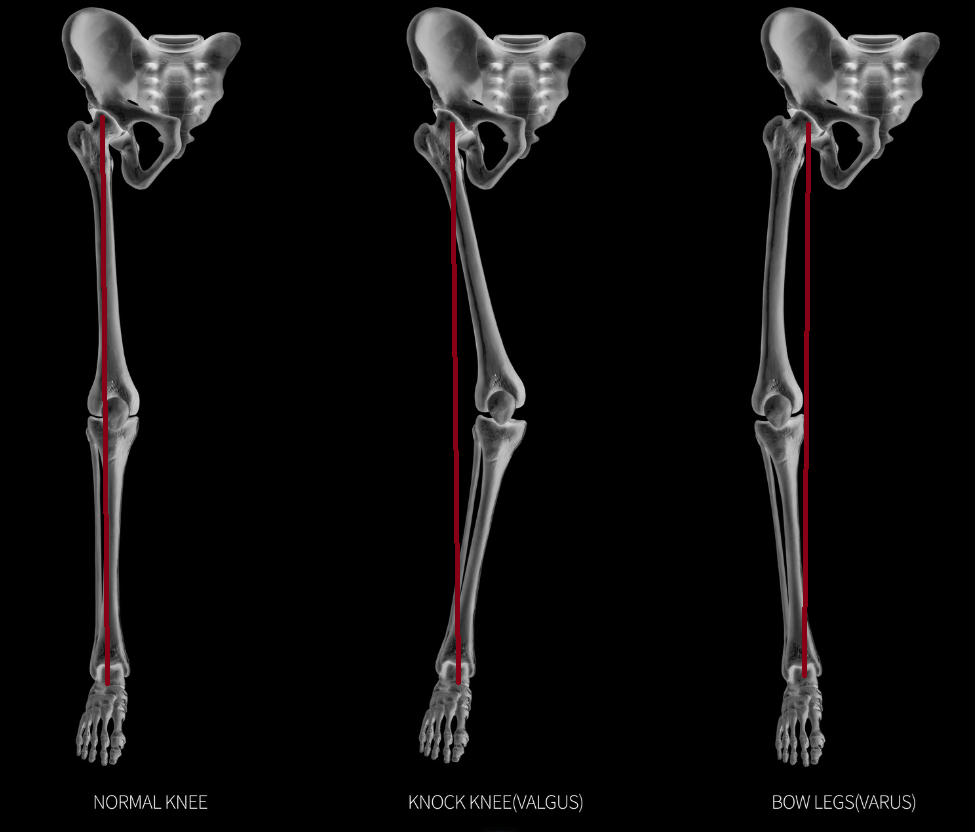
Personalized alignment in knee replacement — the short answer
Personalized alignment is a way of positioning a total knee replacement to match your natural leg alignment, ligament balance, and soft-tissue envelope, rather than forcing every knee to one neutral mechanical target. It is an option for most primary knee replacements. Dr. Morton plans it on a 3D model and executes it with robotic assistance on every knee, within published "safe zone" limits. Early studies suggest a more natural-feeling knee; long-term durability data are still accumulating. Individual results vary.
- Goal: a knee that moves the way yours naturally did, not just a straight leg on X-ray
- How: a 3D plan from imaging, executed and verified by the robot within fractions of a degree
- Evidence: early studies suggest a more natural-feeling knee, with short-term outcomes equal to or modestly better than mechanical alignment
- Guardrail: alignment is kept within a published safe zone to protect the implant from loosening
- Where: The Queen's, Adventist Health Castle, and Hilo Community Surgery Center
What is personalized alignment?
Personalized alignment is a patient-specific approach to knee replacement that customizes where and how the implant is placed to match your individual anatomical structure. Instead of relying on a one-size-fits-all technique, the surgeon accounts for the natural alignment of your leg, the balance of your ligaments, and the constraints of your soft tissues — so the implant fits the knee you were born with.
Advanced imaging such as CT scans, MRI, or digital X-rays is used to build a detailed 3D model of your knee before surgery. That model guides the implant's placement in the operating room. The goal is simple: restore the knee's natural movement while reducing stress on the surrounding tissues.
How it differs from traditional mechanical alignment
Traditional knee replacement follows a generalized mechanical alignment: the implant goes into a fixed, neutral position calculated the same way for every patient. It is a proven, effective method — but it does not accommodate the real differences in knee structure from one person to the next. No two legs are aligned identically, and forcing every knee to the same target can leave some patients with a joint that works well on X-ray but never quite feels like their own.
| Question | Mechanical alignment | Personalized alignment |
|---|---|---|
| Where does the implant go? | A fixed, neutral position — the same target for everyone | A position tailored to your natural leg alignment |
| What guides the plan? | Standardized cutting angles | A 3D model of your knee from CT, MRI, or digital X-rays |
| How are soft tissues handled? | Ligaments are released to fit the implant position | Implant position respects your ligament balance and soft-tissue envelope |
| What is the aim? | A straight leg on X-ray | A knee that moves the way yours naturally did |
The benefits — and what the evidence actually shows
Tailoring the implant to your anatomy aims at several advantages over the standardized approach:
- Better function and feel. Early studies suggest a knee aligned to its own anatomy moves through a more natural range of motion, with less discomfort in movement and an easier return to daily activities. This is the most consistent finding so far — short-term patient-reported outcomes equal to, or modestly better than, mechanical alignment.
- Fewer soft-tissue releases. Respecting your native ligament balance means fewer ligaments have to be cut or stretched to fit the implant — which is also what the robot measures and controls during surgery.
- Possibly faster early recovery. Because personalized alignment preserves more of the knee's natural biomechanics, some patients report less pain and greater mobility soon after surgery. Alongside the quad-sparing approach and tourniquet-free technique, it is one contributor among several to a quicker recovery.
- Durability — planned inside the safe zone. In theory, aligning the knee the way it naturally loaded spreads force more evenly across the implant. Because alignment pushed far outside a knee's natural range can stress the tibial component, the plan is always kept within published "safe zone" boundaries rather than chasing native alignment at any cost — and what actually determines implant durability still applies.
The procedure, step by step
Personalized alignment combines advanced technology with careful planning. Here is how it unfolds:
- Before surgery
Pre-surgical planning
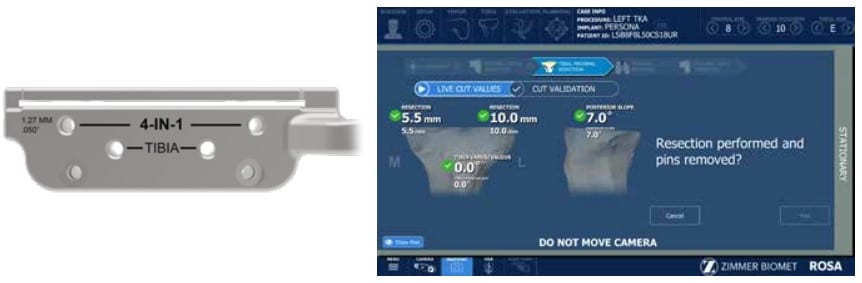
Imaging — calibrated standing X-rays, or CT for some platforms — builds a 3D model. The implant position that best restores your anatomy is planned on that model, within safe-zone limits.
- In the OR
Precision execution
The robot positions cutting guides to the plan, measures ligament balance through motion, and verifies each cut — so the implant lands where the plan says.
- After
Recovery tailored to you
With natural mechanics preserved and fewer releases, rehabilitation is adapted to your knee; walking starts the day of surgery.
Trade-offs worth knowing
Personalized alignment is not without considerations, and an honest discussion covers them:
- Cost. The advanced imaging and robotic technology behind personalized techniques can add to the overall cost of surgery. It is worth understanding what your knee replacement will actually cost before you decide.
- Technology access. The required tools and software are not available at every facility, which limits access to personalized alignment in many places.
- Surgeon expertise. The result depends heavily on the surgeon's skill and experience with these techniques. Seek out a surgeon who is genuinely proficient in customized knee replacement — not one trying it for the first time.
In Hawai'i, those last two barriers are lower than patients often assume. Dr. Morton is certified on all four major surgical robots — ROSA, Mako, CORI, and VELYS — and performs robotic-assisted knee replacement at The Queen's Medical Center in Honolulu, Adventist Health Castle, and the Hilo Community Surgery Center, which brings Mako robotic technology to the Big Island.
References
- Lustig S, Sappey-Marinier E, Fary C, Servien E, Parratte S, Batailler C. Personalized alignment in total knee arthroplasty: current concepts. SICOT-J. 2021;7:28. Source
- Massé V, Cholewa J, Shahin M. Personalized alignment for total knee arthroplasty using the ROSA Knee and Persona knee systems: surgical technique. Front Surg. 2023;9:1098504. Source
- von Eisenhart-Rothe R, Lustig S, Graichen H, et al. A safe transition to a more personalized alignment in total knee arthroplasty: the importance of a "safe zone" concept. Knee Surg Sports Traumatol Arthrosc. 2022;30(2):365–367. Source
- Vendittoli PA, Riviere C, Hirschmann MT, Bini S. Why personalized surgery is the future of hip and knee arthroplasty: a statement from the Personalized Arthroplasty Society. EFORT Open Rev. 2023;8(12):874–882. Source
Is personalized alignment right for your knee?
Personalized alignment is becoming a preferred way to plan knee replacement for surgeons with the tools to execute it. By working with each patient's anatomy rather than against it, the approach aims to improve how the knee feels and functions, reduce soft-tissue releases, and support recovery — while staying inside limits that protect the implant. It is part of Dr. Morton's complete knee replacement protocol in Hawai‘i — robotic on every knee, quad-sparing, tourniquet-free — rather than an upgrade you have to request.
If you are weighing knee replacement, schedule an orthopedic consultation at any of Dr. Morton's four Pacific Bone & Joint clinics — Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo, or Kona — or call (808) 439-6201. Most new patients are seen within one to two weeks. Bring a photo ID, your insurance card, a list of current medications, and any prior imaging or operative reports; if your X-rays were taken in Hawai‘i, the office can usually retrieve them electronically, and new standing X-rays are taken in the clinic at the same visit. Managed-care and Medicaid/Quest plans may need a referral from your primary care physician — the office checks before your visit. When an in-person visit isn't practical — a neighbor island without a nearby clinic, or a patient traveling from across the Pacific — a telehealth visit with existing X-rays can start the process.
- You may be a candidate if standing X-rays show bone-on-bone arthritis and nonsurgical care has been tried
- You may be a candidate if you are having a first-time total knee replacement — most primary knees qualify
- Planned more conservatively if your native alignment falls outside the published safe zone — the plan is restricted, not abandoned
- Usually not the framework for revision knee replacement, where exposure and fixation drive the plan
Medically reviewed by Paul Norio Morton, MD, FAAOS, FAAHKS. Last reviewed: . This article is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.