
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
The short answer: most knee replacements succeed
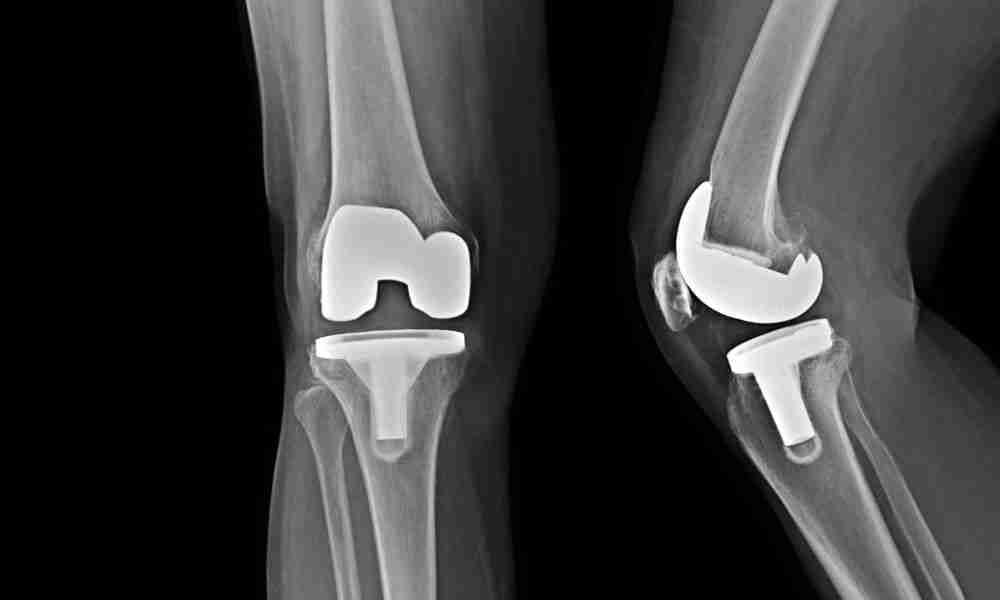
Studies report that 75–90% of patients have significant pain relief and improved function ten years after a total knee replacement. Measured by the implant itself, the numbers are even stronger: about 98% of knee replacements are still functioning at ten years, and more than 80% are still going at twenty.
That track record is why hundreds of thousands of knee replacements are performed in the United States every year, and why the operation is consistently rated among the most effective in all of medicine for restoring quality of life. But notice that those two sets of numbers aren't the same — and the gap between them is the honest part of this article. An implant can be perfectly fixed to bone, a "success" on every X-ray, while its owner still wishes the knee felt more natural. Understanding what each number actually measures is the first step to stacking the odds in your favor.
One more thing the headline numbers hide: outcomes are not just the result of the surgery itself. They are shaped by the techniques and technologies wrapped around it — how the components are aligned, how pain is managed, whether a tourniquet is used, how soon you're up and moving, even what you eat while you heal. Each of those is a lever, and this page walks through how Dr. Morton pulls every one of them.
Pain, function, satisfaction: three different yardsticks
"Success" hides three separate questions. Survivorship asks whether the implant is still in place and working — no loosening, no revision surgery. That's where the 98%-at-ten-years figure comes from. Pain and function ask whether the knee hurts less and does more: walking, stairs, work, travel — in short, whether you can return to normal activities without pain. Most patients improve dramatically on both counts, which is where the 75–90% figure lives. Satisfaction asks something more personal — did the knee meet the expectations you carried into the operating room?
A knee can pass the first two tests and still miss the third. That's why expectations deserve as much consultation time as the surgery itself. A replaced knee is a very good knee, but it is a mechanical one: it may feel different from the knee you had at twenty-five, click occasionally, or dislike kneeling on hard ground. Patients who know that going in are consistently the happiest coming out.
The dissatisfied minority — and what drives it
Up to 20% of patients report some dissatisfaction after total knee replacement. The field takes that number seriously — it drives most revision workups — and the common causes are identifiable. Some are about expectations that were never discussed. Others are physical: residual pain, stiffness that limits bending, a sense of instability, or kneecap problems. Less often, the culprit is a true mechanical issue — a component slightly out of alignment, ligaments left unbalanced — and occasionally infection or early loosening is found.
The practical message is this: persistent pain after a knee replacement is not something to accept or live around. It has a cause, and a systematic evaluation — exam, imaging, blood work, and sometimes joint aspiration — usually finds it. If your knee was replaced elsewhere and still hurts, that structured workup comes first, long before any conversation about revision knee replacement. Some of those knees need surgery; many need an explanation, targeted therapy, or time — but all of them deserve an answer.
What makes success more likely — and what makes it harder
Some knees walk into surgery with better odds than others, and it helps to know which factors are yours to move. Success is more likely when expectations are realistic, the quad is strong going in, weight and blood sugar are reasonably controlled, and you don't smoke. Deformity that is caught before it becomes severe is easier to correct, and a knee that still bends well before surgery usually bends well after it.
The headwinds are just as identifiable: severe stiffness or deformity, prior knee surgery, uncontrolled diabetes, smoking, and long-standing chronic pain conditions that have sensitized the nervous system. None of these disqualifies you — Dr. Morton operates on hard knees routinely — but they change the preparation. Several are modifiable, which means the months before surgery are not just waiting time. Losing weight, building the quad, tightening blood sugar control, and quitting smoking each move your odds in the right direction before the incision is ever made.
How robotics and alignment target the gap
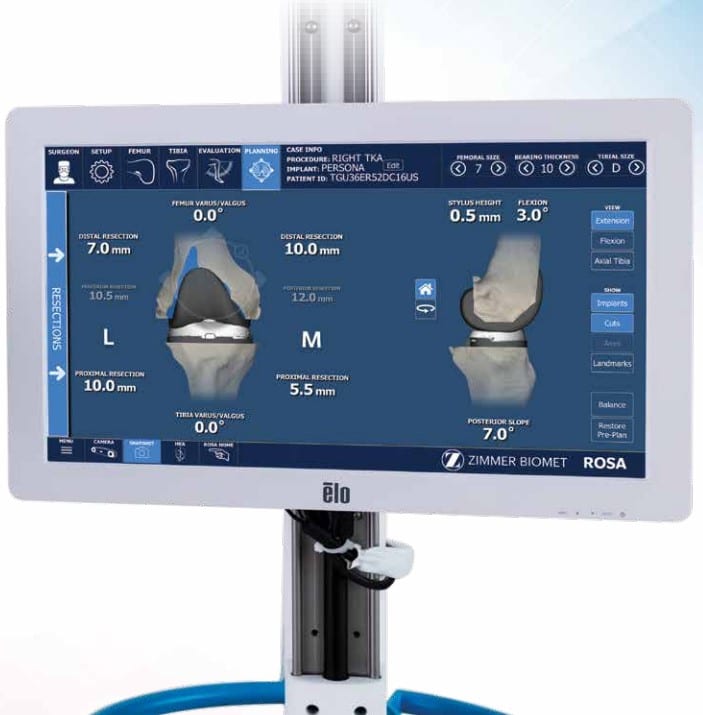
Alignment and soft-tissue balance are two of the few success factors a surgeon fully controls — and they are exactly the factors implicated when a well-fixed knee still doesn't feel right. Precision matters for durability, too: even a slight misalignment concentrates load on one part of the implant, accelerating uneven wear, shortening its lifespan, and setting up the very revision surgery everyone wants to avoid. That's why Dr. Morton plans every knee in 3D and executes the plan with robotic assistance. The robot doesn't operate; it measures your ligament tension in real time and helps position components precisely to a plan personalized to your anatomy, rather than a one-size-fits-all average. A 2022 systematic review and meta-analysis found robotic-assisted knee replacement associated with improved component accuracy and better patient-reported outcomes — evidence that the precision shows up where it counts, in how the knee feels.
Dr. Morton is certified on all four robotic platforms in use today — ROSA, Mako, CORI, and VELYS — so the technology is matched to your knee and your surgical venue, never the other way around. That includes the neighbor islands: the Mako robot at Hilo Community Surgery Center brings robotic knee replacement to the Big Island without a flight to Honolulu.
Technique choices stack on top of that precision. A quad-sparing subvastus approach protects the muscle that powers your recovery, and structured follow-up catches a recovery drifting off track early. None of this guarantees a perfect knee. What it does is remove the preventable reasons for an imperfect one.
The success protocol, at a glance
National averages describe the average operation. Dr. Morton's protocol is built to beat them, one deliberate choice at a time. Each element below has its own evidence base — and each targets a specific, known reason knee replacements disappoint.
| Protocol element | How it moves your odds |
|---|---|
| Robotic assistance (ROSA, Mako, CORI, VELYS) | Precise component alignment and ligament balance — the factors most often implicated when a knee disappoints |
| Spinal anesthesia | Effective pain control from the moment surgery ends |
| Long-acting local anesthetic | Up to 72 hours of relief at the knee itself, covering the hardest days with fewer opioids |
| Iovera cryoneurolysis | Nerves around the knee are treated before surgery; relief can last up to 90 days |
| No tourniquet | Avoids the muscle damage and thigh pain that delay recovery |
| No drains | Lower infection risk, less discomfort, smoother healing |
| Same-day discharge | Recovery at home — higher satisfaction, fewer complications, less exposure to hospital-acquired infection |
| Recovery nutrition | Protein and amino acids to rebuild the muscle that powers rehabilitation |
Pain control that outlasts the hospital stay
Pain management isn't a comfort measure bolted onto the surgery — it is a success factor in its own right, because a knee that hurts less moves sooner, and early motion is the foundation of a good result. Dr. Morton layers three techniques so that relief hands off smoothly from one to the next.
Spinal anesthesia provides effective pain control from the moment surgery ends. Long-acting local anesthetics infiltrated around the knee then take over, delivering relief for up to 72 hours — through the days that are traditionally the hardest. In a randomized controlled trial, this approach improved postoperative outcomes after knee replacement. Together they sharply reduce the need for opioid painkillers, and with it the risk of dependency.
Iovera cryoneurolysis starts working before the operation does. This FDA-cleared treatment precisely freezes the sensory nerves around the knee ahead of surgery, quieting pain signals for weeks — relief can last up to 90 days. Studies show it reduces post-surgical opioid use and speeds the return to daily activities. Learn more about iovera treatment and Dr. Morton's broader opioid-sparing approach to surgery.
No tourniquet, no drains — and home the same day
Traditional knee surgery inflates a tourniquet around the thigh to limit bleeding and leaves a drain in the wound afterward. Dr. Morton avoids both wherever possible, because the evidence says they cost more than they give. A prospective randomized trial found tourniquet use linked to muscle damage and pain that can delay recovery — you feel it as a deep thigh ache that makes the quad reluctant to fire, exactly when you need it most. Skipping the drain reduces infection risk and discomfort, promoting a smoother, faster healing process.
Those choices, combined with modern anesthesia and robotic efficiency, are what make same-day knee replacement safe for most healthy patients. Going home the day of surgery is more than a convenience: studies link fast-track joint replacement to higher patient satisfaction, and recovering at home reduces exposure to hospital-acquired infections. Dr. Morton's own outcomes data mirrors the literature — his same-day patients report higher satisfaction and fewer complications.
Where your surgery happens is matched to your health and your island: The Queen's Medical Center or Adventist Health Castle on O‘ahu — with same-day discharge for streamlined cases — and Hilo Community Surgery Center for Big Island patients.
Nutrition: the success factor most patients never hear about
Surgery is a controlled injury, and healing from it is a construction project — one that consumes raw materials. After a knee replacement your body's protein requirements rise above normal to repair tissue, support immune function, and rebuild the muscle around the new joint. Patients who don't meet that demand heal with the brakes on.
- Protein supplies the building blocks for regenerating muscle and the structural tissues around the knee.
- Arginine and glutamine — two specific amino acids — play documented roles in wound healing and immune function, and supplementation helps patients who can't meet their needs through diet alone.
- Branched-chain amino acids (BCAAs) support muscle recovery during the weeks when activity is limited.
The evidence is practical: protein and amino acid supplementation helps preserve muscle mass during periods of reduced mobility — exactly the situation after knee surgery — and studies report faster recovery with better pain and mobility outcomes in supplemented patients. Because appetite is often poor in the first weeks and cooking is a chore on a healing knee, Dr. Morton recommends a surgery-specific blend designed for easy digestion and rapid absorption, in convenient shake or powder form. Details are on the recovery nutrition page.

Your half of the success equation
Half of a great outcome happens outside the operating room. The strongest predictors you control are the shape you arrive in, the therapy you do afterward, and the expectations you bring to surgery. The recovery timeline rewards consistency over intensity — patients who do the unglamorous daily work of straightening, bending, and walking almost always land in the satisfied majority. The first six weeks matter most: range of motion earned early is kept for life, while stiffness allowed to set in is hard to win back.
If you're weighing surgery, the best next step is a frank conversation about your knee, your goals, and your realistic odds. Schedule a consultation and bring every hard question you have — the honest answers are the ones worth operating on.
- Strengthen the quad and hip before surgery — better in, better out
- Commit to physical therapy, especially in the first six weeks
- Keep weight and blood sugar controlled to lower infection risk
- Eat enough protein while you heal — recovery is a construction project
- Set expectations with your surgeon before the operation, not after
- Keep follow-up visits so small problems are caught while they're small
References
- Rodriguez-Merchan EC. Patient satisfaction following primary total knee arthroplasty: contributing factors. Arch Bone Jt Surg. 2021;9(4):379–386.
- Zhang J, et al. Robotic-arm assisted total knee arthroplasty is associated with improved accuracy and patient reported outcomes: a systematic review and meta-analysis. Knee Surg Sports Traumatol Arthrosc. 2022;30(8):2677–2695.
- Malige A, et al. Liposomal bupivacaine in adductor canal blocks before total knee arthroplasty leads to improved postoperative outcomes: a randomized controlled trial. J Arthroplasty. 2022;37(8):1549–1556.
- Zhao HY, et al. The effect of tourniquet use on total blood loss, early function, and pain after primary total knee arthroplasty: a prospective, randomized controlled trial. Bone Joint Res. 2020;9(6):322–332.
- Jansson MM, et al. Patients' satisfaction and experiences during elective primary fast-track total hip and knee arthroplasty journey: a qualitative study. J Clin Nurs. 2020;29(3–4):567–582.
- Roth ZA, et al. Preoperative cryoneurolysis for total knee arthroplasty: a case series. J Perianesth Nurs. 2023;38(1):33–38.
Medically reviewed by Paul Norio Morton, MD, FAAOS, FAAHKS. Last reviewed: . This article is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.